Prefeitura de Bento Gonçalves – RS abre inscrições para Concurso com mais de 100 vagas

Concurso Público em Bento Gonçalves/RS oferece mais de 100 vagas


A Prefeitura de Bento Gonçalves, Rio Grande do Sul, divulgou a realização de um novo Concurso Público.

As vagas do certame estão distribuídas de acordo com os seguintes níveis de escolaridade:

  • Nível Fundamental Completo e Incompleto: Auxiliar de Serviços de Obras (2); Eletricista (1); Motorista (1); Motorista de Ambulância (CR); Operador de Máquina (2); Servente (CR); Auxiliar Administrativo (5); Higienizador (2); e Mecânico (CR).
  • Nível Médio Completo e Incompleto: Auxiliar de Odontologia (1); Agente Municipal de Trânsito (5); Agente Tributário (1); Assessor Administrativo (2); Auxiliar de Educação Infantil (16); Auxiliar de Farmácia (1); Cuidador (5); Educador Social (2); Fiscal de Obras e Posturas (1); Fiscal do Meio Ambiente (1); Fiscal Sanitário (1); Fiscal Tributário (1); Técnico Tributário (1); e Tesoureiro (CR).
  • Nível Técnico: Fiscal Epidemiológico (CR); Técnico em Contabilidade (CR); Técnico em Enfermagem (2); Técnico em Informática (1); Técnico em Radiologia (CR); Técnico em Segurança do Trabalho (1); Técnico em Turismo (CR); e Topógrafo (CR).
  • Nível Superior: Advogado (CR); Analista de Sistemas e Programas (1); Arquiteto (1); Assistente Social (1); Auditor de Tributos Municipais (1); Biblioteconomista (CR); Biólogo (CR); Bioquímico (CR); Contador (1); Educador de Escola Infantil (1); Enfermeiro (2); Enfermeiro do Trabalho (CR); Engenheiro Agrônomo (CR); Engenheiro Ambiental (CR); Engenheiro Civil (1); Engenheiro Químico (CR); Farmacêutico (CR); Fisioterapeuta (CR); Fonoaudiólogo (CR); Geólogo (CR); Gestor Público (CR); Médico nas especialidades de Anestesista (1); Cardiologista (1); Cirurgião Geral (1); Clínica Médica (2); Dermatologista (1); do Trabalho (1); Endocrinologista (CR); Gastroenterologista (CR); Geral Comunitário (7); Ginecologista/Obstetra (2); Infectologista (CR); Neurologista (1); Oftalmologista (1); Ortopedista/Traumatologista (3); Otorrinolaringologista (1); Pediatra (2); Pneumologista (1); Psiquiatra (1); Radiologista (1); Urologista (1); Museólogo (CR); Nutricionista (1); Odontólogo (1); Orientador Educacional (1); Professor de Anos Finais nas disciplinas de Artes (1); Ciências (1); Educação Física (1); Geografia (1); História (1); Inglês (1); Matemática (1); Português (1); Anos Iniciais (1); Anos Iniciais – Educação Física (1); Psicólogo (2); Publicitário (CR); Supervisor Escolar (1); e Terapeuta Ocupacional (1).

As jornadas dos profissionais serão desempenhadas em até 40 horas, e os salários variam de R$ 809,39 a R$ 4.678,07.

Os interessados devem se inscrever no site www.fdrh.rs.gov.br, até 28 de abril de 2016. As taxas custam R$ 50,00, R$ 70,00 e R$ 100,00 e o pagamento deve ser efetuado via boleto bancário.

A classificação dos candidatos ocorre por meio de Provas Objetivas, de Títulos e Prática

Conteúdos relacionados

Taping: tipos, aplicações e evidências na fisioterapia

Taping: tipos, aplicações e evidências na fisioterapia

Introdução

A taping é comumente usada por fisioterapeutas para:

alivie sua dor
melhorar a estabilidade da articulação
aumentar a confiança do atleta
reduzir a recorrência de lesões
prevenir ferimentos

Existem diferentes tipos de taping que podem ser utilizados:

A taping de cintagem rígida comumente usada em bandas ou cintas é freqüentemente referida como “taping esportiva” ou “taping atlética” e é mais frequentemente um estilo rígido de taping de cintagem.
A taping de cintagem elástica também pode ser usada quando menos rigidez ou suporte são necessários.
A taping cinesiológica é uma versão aprimorada da fita elástica esportiva que atua para auxiliar dinamicamente a função muscular.

taping como aplicar

A taping pode ser usada para:

estabilizar ou apoiar uma lesão
aliviar a dor descarregando estruturas vulneráveis ​​ou doloridas
facilitar o movimento normal, a ação muscular ou os padrões posturais.
Tipos de gravação
Kinesio Taping


Confira tambem

Teste de Yeoman

Bandagem elástica: descubra para que serve esse acessório


Kinesiology taping (KT) é uma ferramenta terapêutica e tem se tornado cada vez mais popular na arena esportiva. A fita adesiva tem sido usada há muito tempo para a prevenção e tratamento de lesões esportivas. KT não é usado apenas para lesões esportivas, mas para uma variedade de outras condições. Foi desenvolvido pelo quiroprático japonês na década de 1970 com a intenção de aliviar a dor [1] e melhorar a cicatrização dos tecidos moles [2]. Existem muitos benefícios propostos para KT, incluindo: facilitação proprioceptiva; fadiga muscular reduzida; facilitação muscular; redução da dor muscular de início tardio; inibição da dor; cura intensificada, como redução do edema e melhora da drenagem linfática e do fluxo sanguíneo [3].

Mulligan Taping

A Mobilização com Movimento (MWM) desenvolvida por Brian Mulligan FNZSP (Hon) da Nova Zelândia é reconhecida mundialmente em abordagens de terapia manual. Seu conceito é a aplicação de deslizamento articular acessório aplicado manualmente com movimento ativo sem dor concomitante. Durante o desenvolvimento dos MWMs, Brian Mulligan descobriu que o tratamento em alguns pacientes foi aprimorado quando ele utilizou a fita adesiva para complementar as forças direcionais fornecidas após a sessão de tratamento com MWM. A bandagem é aplicada em direções que complementam a força passiva MWM aplicada a uma articulação ou tecido mole.

McConnell Taping

A bandagem McConnell (também conhecida como bandagem patelar) é frequentemente usada para tratar pacientes com dor anterior do joelho, mais especificamente com pacientes com condromalácia patelar e síndrome da dor patelofemoral [4]. A fita corrige o rastreamento da patela dentro do sulco patelar medializando a patela. A técnica também alonga os tecidos moles laterais e fortalece o vasto medial oblíquo [5].

Referências

  1. Liu YH, Chen SM, Lin CH, Huang CI, Sun YN. Rastreamento de movimento no tecido do cotovelo a partir da sequência de imagens ultrassônicas para pacientes com epicondilite alteral. Procedimentos da 29ª Conferência Internacional Anual do IEEE EMBS Cite Interbationale, Lyon, França, 2007.
  2. Kahanov L. Kinesio taping, Part 1: Uma visão geral de seu uso em atletas.Athletic Therapy Today 2007; 12: 17-18.
  3. Basset KT, Lingman SA, Ellis RF. O uso e a eficácia do tratamento com bandagem cinestésica para doenças musculoesqueléticas: uma revisão sistemática. New Zealand Journal of Physiotherapy 2010; 38 (2): 56-62.
  4. Derasari A. et al. A bandagem de McConnell desloca a patela inferiormente em pacientes com dor patelofemoral: um estudo de imagem por ressonância magnética dinâmica. Jornal da associação americana de fisioterapia. Março de 2010. 90 (3): 411-419
  5. Naoko Aminaka e Phillip A Gribble; Uma revisão sistemática dos efeitos da bandagem terapêutica na síndrome da dor femoropatelar; Jornal de treinamento atlético; 2005 out – dez; 40 (4): 341-351

Confira um artigo sobre a taping

Evidência preliminar de que a taping não otimiza o acoplamento das articulações do pé e tornozelo em pacientes com instabilidade crônica do tornozelo.

Objetivo:

O movimento pé-tornozelo é afetado pela instabilidade crônica do tornozelo (IAC) em termos de cinemática alterada. Este estudo centra-se na multissegmentar pé-tornozelo movimento e junta de acoplamento em descalço e CAI gravadas pacientes durante os três subfases de postura em correr.

MÉTODOS:

Os dados do movimento segmentar do pé de 12 controles e 15 participantes do CAI durante a corrida com um padrão de golpe de calcanhar foram coletados por meio da análise da marcha. Os participantes do CAI realizaram testes de corrida em três condições, corrida descalça e corrida com alta e baixa concentração de corante. As variáveis ​​dependentes foram a amplitude de movimento (RoM) ocorrendo nos diferentes ângulos intersegmentos, bem como os coeficientes de correlação cruzada entre segmentos predeterminados.

RESULTADOS:

Não houve diferenças significativas de RoM para corrida descalça entre pacientes com CAI e controles. Em condições com taping, as duas primeiras subfases mostraram apenas alterações de RoM no mediopé sem redução aparente de RoM em comparação com a condição CAI descalço. Na última subfase, houve redução limitada de RoM no meio e no retropé. Os coeficientes de correlação cruzada destacaram uma tendência para um acoplamento articular mais fraco na condição CAI descalço em comparação com os controles. O acoplamento da junta nas condições CAI gravadas não mostrou otimização em comparação com a condição CAI descalço.

CONCLUSÕES:

A RoM não foi significativamente alterada para corrida descalça entre pacientes com CAI e controles. Em condições com taping, não houve tendência distinta para valores de RoM médios mais baixos devido às restrições mecânicas da taping. O acoplamento da articulação em pacientes com CAI não foi otimizado por bandagem.

Conteúdos relacionados

Espirometria: Guia Completo para Fisioterapeutas

Espirometria: Guia Completo para Fisioterapeutas

Descrição

Spirometry1.jpg EspirometriaIr para: navegação, pesquisa 300px Spirometry1

A espirometria é um dos testes de função pulmonar ; são investigações úteis no manejo de pacientes com doença respiratória ou fraqueza respiratória secundária a comprometimento neurológico. Eles auxiliam no diagnóstico, ajudam a monitorar a resposta ao tratamento e podem orientar as decisões sobre tratamentos e intervenções adicionais. [1] A espirometria pode medir todos os volumes pulmonares, exceto o volume residual.

Indicação

  • Investigação de pacientes com sintomas/sinais/investigações que sugiram doença pulmonar (por exemplo, tosse, sibilos, falta de ar, crepitações ou anormal )
  • Monitorar pacientes com doença pulmonar conhecida quanto à progressão e resposta ao tratamento (por exemplo , fibrose intersticial , DPOC , asma ou )
  • Investigação de pacientes com doenças que podem ter complicações respiratórias (por exemplo, distúrbios do tecido conjuntivo ou doenças neuromusculares)
  • Avaliação pré-operatória prévia à ressecção pulmonar, cirurgia abdominal ou cirurgia cardiotorácica.
  • Avaliar pacientes em risco de doenças pulmonares (por exemplo, exposição a toxinas pulmonares, como radiação, medicação ou exposição ambiental ou ocupacional)
  • Vigilância após transplante de pulmão para avaliar rejeição aguda, infecção ou bronquiolite obliterante [1]

Contra-indicações

  • Aneurisma
  • Hemoptise de origem desconhecida
  • Pneumotórax
  • Estado cardiovascular instável, infarto do miocárdio recente ou
  • Distúrbios agudos que afetam o desempenho do teste, como náusea ou vômito
  • Procedimentos cirúrgicos torácicos ou abdominais recentes
  • Cirurgia ocular
  • Derrame pleural
  • Pós-MI. [1] [2] [3]

Protocolo

Calibração

Antes de realizar a espirometria, o equipamento utilizado deve ser calibrado, ou pelo menos a calibração verificada no início da sessão. Os procedimentos de calibração diferem entre os dispositivos. Leia as instruções associadas ao seu espirômetro para obter mais informações. Alguns medidores precisam ser devolvidos ao fabricante para reparo se a calibração estiver incorreta. É uma boa prática que os valores espirométricos sejam verificados semanalmente usando um controle biológico (uma pessoa saudável trabalhando em sua equipe). [3]

Posicionamento do paciente

A postura correta de medição é a seguinte:

  • Sentado na posição vertical: há uma diferença na quantidade de ar que o paciente pode exalar da posição sentada em comparação com a posição em pé, desde que esteja sentado em linha reta e não haja restrições [4] e a posição em pé é melhor que a deitada mentindo [5]
  • Pés apoiados no chão com as pernas descruzadas: não há uso dos músculos abdominais para a posição das pernas.
  • Afrouxe roupas apertadas
  • Dentaduras normalmente deixadas: é melhor ter alguma estrutura na área da boca, a menos que as dentaduras estejam muito soltas.
  • Use uma cadeira com braços: ao expirar ao máximo, os pacientes podem ficar tontos e possivelmente oscilar ou desmaiar.

No ambiente hospitalar, pode ser impossível para o paciente sentar em uma cadeira, portanto, a posição do paciente (geralmente em decúbito dorsal) deve ser a mesma e documentada para testes futuros. [3]

Técnica

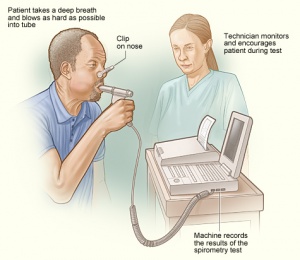
Existem várias técnicas diferentes para realizar a espirometria. No entanto, mais comumente o paciente inspira profundamente, o mais forte possível, e sopra o mais forte e rápido possível e continua até que não haja mais ar. O PEF é obtido a partir da manobra FEV1 e FVC.

O incentivo faz uma grande diferença, então não tenha medo de levantar a voz para encorajar o paciente, principalmente perto do final da manobra. O paciente precisa continuar soprando até que não saia mais ar. Alguns pacientes, particularmente aqueles com doença obstrutiva, podem achar difícil expirar completamente em uma manobra forçada. [3]

Qualidade

Uma manobra aceitável é definida como segue:

  • Um início explosivo (sem hesitação ou curva sigmóide) com um volume de retroextrapolação [1]
  • A manobra foi realizada com inspiração e expiração máximas.
  • Não ocorreu fechamento da glote ou interrupção do fluxo aéreo durante a manobra (por exemplo, por hesitação ou bloqueio do bocal).
  • Sem tosse (principalmente durante o primeiro segundo), inspirações durante o rastreamento ou evidência de vazamentos.

O melhor VEF 1 e CVF podem ser obtidos em diferentes manobras.

Pode haver problemas de reprodutibilidade: a expiração forçada pode causar broncoconstrição, portanto, deve haver ≥30 segundos entre as manobras. Para alguns pacientes, particularmente asmáticos, podem ser necessários vários minutos. [3]

Definições de medição [3]

Volume expiratório forçado em um segundo (VEF 1 ) O volume de ar que é exalado à força após inspiração completa no primeiro segundo.
Capacidade vital forçada (CVF) O volume de ar que é exalado à força após inspiração completa.
A proporção dos dois volumes (VEF1/CVF) Este cálculo permite a identificação de defeitos ventilatórios obstrutivos ou restritivos. FEV1/FVC 70% onde a FVC é mais reduzida do que o FEV1 é visto na patologia restritiva.
Capacidade vital (VC) A quantidade máxima de ar que pode ser exalada ao soprar o mais rápido possível
Pico de fluxo expiratório (PFE) O fluxo máximo que pode ser exalado ao soprar a uma taxa constante

Referências

  1. ↑ 1,0 1,1 1,2 1,3 Ranu, H., Wilde, M., & Madden, B. (2011). Testes de Função Pulmonar. The Ulster Medical Journal ,  80 (2), 84-90.
  2. ↑ Cooper BG Uma atualização sobre as contraindicações para testes de função pulmonar Thorax 2011;66:714-723.
  3. ↑ 3,0 3,1 3,2 3,3 3,4 3,5 Moore VC. Espirometria: passo a passo. Respirar. 1 de março de 2012;8(3):232-40.
  4. ↑ Patel AK, Thakar HM. Valores espirométricos na posição sentada, em pé e supina. J Pulm Pulm Respir Res. 2015; 2(1): 00026. DOI: 10.15406/jlprr.2015.02.00026
  5. ↑ Melam G, Buragadda S, Alhusaini A, Alghamdi M, Alghamdi M, Kaushal P. Efeito de diferentes posições nas medições de CVF e VEF1 de pacientes asmáticos. Jornal da ciência da fisioterapia.2014; 26(4) 591-593. 10.1589/jpts.26.591.

Conteúdos relacionados

Papel dos Fisioterapeutas na UTI

Papel dos Fisioterapeutas na UTI

Introdução

Cuidados críticos são os cuidados especializados de pacientes cujas condições ameaçam a vida e que requerem atenção integral e monitoramento constante, geralmente em unidades de terapia intensiva (UTI).

Pacientes críticos frequentemente sofrem complicações físicas e psicológicas de longo prazo. Eles estão em ventilação mecânica de longo prazo e, como resultado, 25% apresentam fraqueza muscular significativa e aproximadamente 90% dos sobreviventes de UTI de longo prazo terão fraqueza muscular contínua. Permanências prolongadas na unidade de terapia intensiva também estão associadas a qualidade de vida prejudicada, declínio funcional e aumento da morbidade, mortalidade, custo dos cuidados e tempo de internação hospitalar. [1]

Portanto, eles exigem uma equipe multidisciplinar em cuidados intensivos, que é exclusivamente qualificada com habilidades e conhecimentos para trabalhar com a avaliação e manejo de complicações respiratórias, descondicionamento físico e condições neuromusculares e musculoesqueléticas.

O tratamento fisioterapêutico como parte de uma abordagem multidisciplinar do cuidado é integral na promoção da função pulmonar, reduzindo a incidência de pneumonia associada à ventilação mecânica, facilitando o desmame e promovendo alta segura e precoce da unidade de terapia intensiva.

Fisioterapia Reabilitação em UTI

A fisioterapia é uma intervenção importante que previne e atenua os efeitos adversos do repouso prolongado no leito e ventilação mecânica durante a doença crítica. A reabilitação fornecida pelo fisioterapeuta é adaptada às necessidades do paciente e depende do estado de consciência, estado psicológico e força física do paciente. Incorpora qualquer terapia ativa e passiva que promova o movimento e inclua a mobilização. A fisioterapia progressiva precoce, com foco na mobilidade e na marcha ventilada, é essencial para minimizar o declínio funcional.

Efeitos adversos da permanência na UTI:

  • Inatividade física levando a atrofia muscular e fraqueza generalizada
  • Fraqueza diafragmática devido à ventilação mecânica prolongada
  • Úlceras de Pressão
  • função cardíaca e respiratória comprometida
  • trombose venosa profunda
  • infecções

O fisioterapeuta trabalha para manter e melhorar as funções respiratórias e cardíacas e posteriormente auxiliar na reabilitação.

Metas de curto prazo:

  • Atividade precoce – Tanto passiva quanto ativa para manter a integridade do sistema musculoesquelético
  • Posicionamento de pacientes: Para permitir que a gravidade ajude a drenagem do escarro dos pulmões.
  • Técnicas manuais, como agitação e vibrações: são aplicadas nas costelas para tentar soltar e limpar o escarro.
  • Sucção: Colocando um pequeno tubo nos pulmões para sugar o excesso de escarro.
  • Eles desempenham um papel vital no desmame de um paciente da ventilação.

Objetivos de longo prazo:

  • Eles planejam um extenso programa de reabilitação para integrar e reiniciar o paciente na sociedade.
  • Eles estabelecem metas em conjunto com a equipe médica para reabilitar o paciente.

As metas de reabilitação são estabelecidas em comunicação com o paciente, família do paciente e equipe médica e são divididas em curto, médio ou longo prazo e mudam ao longo da recuperação do paciente de uma doença crítica. Eles podem ser tanto físicos quanto psicológicos, mas estão preocupados com as necessidades funcionais do paciente. As metas precisarão ser alcançáveis ​​e baseadas em uma avaliação regular do paciente das consequências físicas e não físicas da doença crítica ao longo de sua recuperação e mudar de acordo com o progresso. [2]

Técnicas de fisioterapia em UTI

Fisioterapia Respiratória:

O papel do fisioterapeuta respiratório é auxiliar na desobstrução das vias aéreas dos pacientes, mantendo e melhorando a integridade do sistema respiratório. As intervenções de tratamento incluem:

  • Posicionamento,
  • Educação,
  • Hiperinsuflação manual e ventilatória,
  • Desmame da ventilação mecânica,
  • Ventilação não invasiva,
  • Percussão, vibração, sucção,
  • Fortalecimento dos músculos respiratórios,
  • Exercícios respiratórios e mobilização [3]

Reabilitação

A Mobilização Precoce com foco no retorno às atividades funcionais auxilia na redução do tempo de internação e minimiza o declínio funcional.

As metas são mapeadas com base no estado físico e psicológico do paciente. Durante sua permanência na unidade de terapia intensiva, os fisioterapeutas devem realizar uma breve avaliação clínica

  • determinar o risco do paciente de desenvolver morbidade física e não física.
  • para identificar suas necessidades atuais de reabilitação
  • Para pacientes em risco, iniciar a reabilitação o mais cedo possível clinicamente, que deve incluir:
  1. Medidas para prevenir a morbidade física e não física evitável,
  2. Suporte nutricional
  3. Um programa de reabilitação individualizado e estruturado com revisões de acompanhamento frequentes. Os detalhes do programa de reabilitação estruturado e as revisões devem ser coletados e documentados nos registros clínicos do paciente. [4]

Impacto da Fisioterapia

A intervenção precoce de fisioterapeutas na UTI ajuda

  • Reduza a permanência do paciente na UTI e a permanência hospitalar geral.
  • Prevenir complicações relacionadas à UTI
  • Para melhorar a função e a qualidade de vida a longo prazo [5]

Estudos mostraram que a intervenção da Fisioterapia em Cuidados Intensivos ajudou a reduzir a taxa de mortalidade em 25%. [6]

Referências

  1. ↑ Chartered Society of Physiotherapy, Fisioterapia funciona: cuidados intensivos. Acessado em 06/02/19↑ Rahimi RA, Skrzat J, Reddy DR, Zanni JM, Fan E, Stephens RS, Needham DM. Fisioterapia. 1 de fevereiro de 2013;93(2):248-55.
  2. ↑ Denehy L, Berney S. Revisões de Fisioterapia. 2006;11(1):49.
  3. ↑ Diretriz clínica NICE 83 Desenvolvido pelo Center for Clinical Practice at NICE Data de publicação:  
  4. ↑ ↑ Tomasi CD, Figueiredo F, Constantino L, Grandi R, Topanotti MFL, Giombelli V, Dal-Pizzol F, Ritter C. Efeito benéfico da fisioterapia respiratória em pacientes críticos ventilados por mais de 48 horas: Um ensaio clínico randomizado. Medicina Intensiva. Conferência 23º Congresso Anual da Sociedade Europeia de Medicina Intensiva, ESICM Barcelona Espanha. Data de publicação: setembro de 2010.

Conteúdos relacionados

Anatomia dos Pulmões: Estrutura, Pleura e Relevância Clínica

Anatomia dos Pulmões: Estrutura, Pleura e Relevância Clínica

Introduction and Location

Lung anatomy nci 407.jpg

The lungs, which is the organ for respiration is a paired cone shaped organs lying in the thoracic cavity separated from each other by the heart and other structures in the mediastinum.

Each lung has a base resting on the diaphragm and an apex extending superiorly to a point approximately 2.5 cm superior to the clavicle[1]. It also has a medial surface and with three borders- anterior, posterior and inferior. The broad coastal surface of the lungs is pressed against the rib cage, while the smaller mediastinal surface faces medially. The lungs receives the bronchus, blood vessels, lymphatic vessels and nerves through a slit in the mediastinal surface called the helium, and the structures entering the helium constitutes the lungs root[2].

The right lung is larger and weighs more than the left lung[3][2]. Since the heart tilts to the left, the left lung is smaller than the right and has an indentation called the cardiac impression to accommodate the heart. This indentation shapes the inferior and anterior parts of the superior lobe into a thin tongue-like process called the lingual.

Pleura

Each lung is invested by and enclosed in a serous pleural sac that consists of two continuous membranes.

The visceral or pulmonary pleura invest the lungs,

The parietal pleura line the pulmonary cavities and adhere to the thoracic wall, mediastinum and diaphragm.

Lung pleura.jpg

The parietal pleura consist of four parts: coastal pleura which lines the internal surface of the thoracic wall, mediastinal pleura which lines the lateral aspect of the mediastinum, diaphragmatic pleura which lines the superior surface of the diaphragm on each side of the mediastinum, cervical pleura extends through the superior thoracic aperture into the root of the neck, forming a cup-shaped dome over the apex of the lung[2].

Pleural Cavity

The pleural cavity is the potential space between the visceral and parietal layers of the pleural and it contains a capillary layer of serous pleural fluid which lubricates the pleural surfaces and allows the layers to slide smoothly over each other during respiration. Surface tension created by the pleural cavity provides the cohesion that keeps the lung surface in contact with the thoracic wall[1].  

Lobes and Fissures of the Lungs

Lung Lobes.jpg

Each lung is divided into lobes by fissures.

Both lungs have oblique fissure and the right is further divided by a transverse fissure. The oblique fissure in the left lung separates the superior and the inferior lobe. The oblique and horizontal fissure divides the lungs into superior, middle and inferior lobes. Thus the right lung has three lobes while the left has two.

Each lobe is supplied by a lobar bronchus. The lobes are subdivided by bronchopulmonary segments which are supplied by the segmental bronchi.

Bronchial Tree

All the respiratory passages from the trachea to the respiratory bronchioles are called the tracheobronchial tree[1][2][3]. The trachea divides at the sternal angle into right and left primary bronchus which goes into the right and left lungs. Each bronchus enters the lung at a notch called the hilum. Blood vessels and nerves also connect with the lungs here and together with the bronchus forms a region called the root of the lungs.

The right main bronchus is larger in diameter and more vertical making it directly in line with the trachea than the left main bronchus[2]. Thus swallowed objects that accidentally enter the lower respiratory tract are most likely to become lodged in the right main bronchus[4].

Lung anatomy.jpg

The main bronchi divide into lobar or secondary bronchi within each lung. Two lobar bronchi exist in the left lung, and three exist in the right lung. The lobar bronchi, in turn give rise to segmental or tertiary bronchi. The tertiary bronchi supply the bronchopulmonary segments.

Bronchopulomonary Segment

Functionally, the lung is divided into a series of bronchopulmonary segments. The bronchopulmonary segments are the largest subdivision of a lobe. They are separated from adjacent segments by connective tissue septa and are also surgically resectable. They are 10 bronchopulmonary segments in the left lung and 8-10 in the left lung[5].

The bronchi further divides, finally giving rise to the bronchioles which are less than 1mm in diameter. Each bronchioles divides into 50 to 80 terminal bronchioles, the final branches of respiratory bronchioles. The functional unit of the lungs which is the acinus includes the respiratory bronchioles, alveolar ducts, and sacs and the alveolar[1]. Approximately 16 generations of branching occur from the trachea to the terminal bronchioles[1]. As the air passageways of the lungs become smaller, the structure of their walls changes[3].

Histology of Bronchopulomonary Segment

The major airways from the trachea through the ten generations of bronchi have descending amounts of cartilaginous support surrounded by smooth muscles and elastic fibres, they have goblet cells for mucus production and are lined with ciliated columnar epithelium to facilitate secretion clearance.

The next five generation of bronchioles have no cartilage or goblet cells, but still have elastic tissue and smooth muscle fibres. They lined with ciliated cuboidal epithelium. Relaxation and contraction of the smooth muscles of the bronchi and bronchioles can change the diameter of the air passageways and so change the volume of air moving through them. The alveoli provide a large surface area for gas exchange. The alveolar walls consist of simple squamous epithelium. Also the tissues surrounding the alveoli contain elastic fibres which allow the alveoli to expand during inspiration and recoil during expiration.

The epithelium of the respiratory zone is not ciliated but debris from the air can be removed by macrophages that move over the surface of the cells. Approximately 300 million alveoli are in the lungs. The average diameter of the alveoli is approximately 250um and their walls are extremely thin. There are two types of cells in the alveoli: type I pneumocytes which are thin squamous epithelia cells that forms 90% of the alveoli surface. Most of the gas exchange take place between these cells. Type II pneumocytes are round secretory that produce surfactant, which makes it easier for the alveoli to expand during inspiration[5].

The bronchial arteries arising from the aorta provide blood supply to the non-respiratory airways, pleura, and connective tissue while the pulmonary arteries supply the respiratory units (acini) and participate in gas exchange.

Venous drainage is mainly by the pulmonary veins (right and left superior and inferior pulmonary veins), though the venous of drainage from the walls of the larger bronchi is carried out by the bronchial veins. All four veins (pulmonary veins) drain into the left atrium.

Nerves supply[3]

The lungs and airways are innervated by the branches of sympathetic trunk and vagus nerve[2]. Sympathetic nervous stimulation results in bronchodilation and slight vasoconstriction, while parasympathetic nervous system stimulation results in bronchoconstriction and indirect vasodilation. The function of the lungs is controlled through the respiratory centre with groups of neurons located at the pons and the medulla oblongata, and complex interactions of specialized peripheral central chemoreceptors.

Relevance to Physiotherapy[3][4]

Auscultation of the lungs and percussion of the thorax are important techniques used during physical examination. Auscultation assesses airflow through the tracheobronchial tree into the lungs.

Percussion helps establish whether the underlining tissues are air filled (resonant sound), fluid filled (dull sound) or solid (flat sound).

Based on the anatomy of the bronchial tree, gravity can be used to assist the clearance of bronchial secretions through the use of positioning. Also Bronchial disorders such as tumour and abscesses may be localized in a bronchopulmonary segments and may be surgically removed without disrupting the surrounding lung tissue.

Defences of the Lungs

There are a number of structures that protects the lungs from inhaled organisms and particles:

  • Nasal mucosa and hairs: warm and humidify inhaled air and filter out particle.
  • Goblet cell and bronchial seromucous glands: produce mucous which contain immunoglobulin A, cytokines, and other cytolytic substances, with extensive mucosal production of nitric oxide by the nose and paranasal sinuses; all of these have potent antimicrobial activity, to protect underlining tissues and trap organisms and particles. Bacteria are destroyed by lysozyme in the mucus.  Also additional protection against bacteria is contributed by lymphocytes which populate the lamina propria in large numbers. The lamina propria contain large blood vessels that help to warm the air.
  • Furthermore, the inferior concha has an especially large venous plexus called the erectile tissue. Every 30 to 60 minutes, the erectile tissue on one side becomes engorged and restricts air flow through that fossa, causing air to be redirected through the other nostrils and fossa thus allowing the engorged side to time to recover from drying. The flow of air shifts between the right and the left nostrils once or twice each hour.   Mucous production is increased by inflammation (e.g. in conditions like asthma and bronchitis) and its composition can be altered by diseases.
  • Cilia: structures move nucleus up the carina and the throat through mucocilliary transport.   Mucocilliary transport is impaired by inhalation of toxic gases (e,g cigarete smoke and air pollution), acute inflammation, infection, anaesthesia, etc[6].
  • Type II pneumocytes: produces surfactant which protects underlining tissue and repairs damaged alveoli epithelium.
  • Alveoli macrophages: engulfs foreign matter and bacteria. Their activity can be hindered by cigeret smoke, air pollution, alveolar hypoxia, radiation, corticosteroid therapy, and ingestion of alcohol.
  • B lymphocytes: produce gamma globulin for the production of antibodies to resist infections.
  • Polymorphonuclear leukocytes engulf and kill blood borne gram negative organisms.

Respiratory Membrane and Gaseous Exchange

Resources

References

  1. ↑ 1.01.11.21.31.4 Scanlon, VC, anders, T. Essentials of anatomy and physiology. 6th eds. F.A. Davis. Philadelphia, 2011
  2. ↑ 2.02.12.22.32.42.52.6 Drake, RL, Vogl, W, Mitchell, AW, Gray, H. Gray’s anatomy for Students 2nd ed.  Philadelphia : Churchill Livingstone/Elsevier, 2010.
  3. ↑ 3.03.13.23.33.43.5 Moore, KL, Dalley, AF, Agur, AM. Clinically oriented anatomy. 7th ed. Baltimore, MD: Lippincott Williams & Wilkins, 2014
  4. ↑ 4.04.1 Watchie, J. Cardiovascular and pulmonary physical therapy. A Clinical manual. 2nd eds. Saunders Elservier, 2010
  5. ↑ 5.05.1 Seeley, RR, Stephens, TD, Tate, P. Essentials of anatomy and physiology. 6th eds. Mc Graw-Hill, 2006
  6. ↑ Gaga, M, Viginola, AM, Chanez, P. Upper and lower airways: similarities and differences. European Respiratory Journal. 2001; 18: 1-15.

Conteúdos relacionados

Intervenções para LBP

Intervenções para LBP

Education

Most guidelines suggest education and advice as a key intervention strategy[1][2][3][4][5][6][7].  The common message is that patients should be reassured that they do not have a serious disease, that they should stay as active as possible, progressively increase their activity levels and return to work as soon as possible.  This is particularly relevant for patients with acute back pain who are low risk of disbaility.

The NICE Guidelines[1] summarise many of the available guidelines and state the following:

  • Provide people with advice and information to promote self-management of their low back pain.
  • Offer educational advice that includes information on the nature of non-specific low back pain and encourages the person to be physically active and continue with normal activities as far as possible.
  • Include an educational component consistent with this guideline as part of other interventions, but do not offer stand-alone formal education programmes.
  • Take into account the person’s expectations and preferences when considering recommended treatments, but do not use their expectations and preferences to predict their response to treatments.
  • Advise people with low back pain that staying physically active is likely to be beneficial.
  • Advise people with low back pain to exercise.

The STarT Back Approach also has some advice for us when educating individuals with LBP:

Language and labels

  • Use functional explanations for pain (sprained back, non-serious back pain). Example: “Many people have back pain from time to time but it is rare for this to be caused by a specific problem. Mostly all that is needed is to get your back moving again and things will settle down.
  • ”Avoid “spondylitis, degeneration, crumbling” etc.
  • Can be more specific sometimes, for example sciatica, if this leads to specific management.
  • Avoid investigating in the first place unless it is specifically indicated. However if you do so be aware that the technical terms used in reports often alarm patients. Translate appropriately, examples: “normal for your age ”, “ the changes seen on your scan are like getting grey hair or wrinkles as you get older”

Dealing with distress

  • Suspend pre-judgment
  • Listen carefully / summarize points
  • Plan to address points
  • Care with language and labels
  • Be honest and realistic
  • Do not criticize the opinions of other clinicians who have seen the patient.
  • Provide information

Activity promotion

  • Activity promotion: beneficial, hurt doesn’t equal harm, minimise bed rest
  • Pacing: short, frequent bouts of activity rather than overdoing things and then regretting it the next day, rests between activity, do less than maximal capabilities and increase as tolerated.
  • Return to work as soon as possible, prolonged absence likely to lead to loss of employment. Use fit notes to support return to work and communicate suggestions to the employer. Help the patient negotiate an early return to work if at all possible.

Exercise Therapy

There is now relatively large consensus across the various guidelines that specific back exercises (as opposed to the advice to stay active, including for example walking, cycling) are not recommended for patients with acute low back pain[3].  There are now also more firm recommendations in favour of exercise therapy in patients with subacute and chronic low back pain[3] but there is no evidence that one form of exercise is superior to another[8].  

NICE Guidelines[1] recommend offering a structured exercise programme tailored to the person. Exercise programmes may include aerobic activity, movement instruction, muscle strengthening, postural control and& stretching.  They should comprise up to a maximum of eight sessions over a period of up to 12 weeks, a group supervised exercise programme in a group of up to 10 people or one-to-one supervised exercise programme may be offered if a group programme is not suitable for a particular person.

Delitto [4]et al suggest that clinicians should consider:

  • utilizing trunk coordination, strengthening, and endurance exercises to reduce low back pain and disability in patients with sub-acute and chronic low back pain with movement coordination impairments and in patients post lumbar microdiscectomy. 
  • utilizing repeated movements, exercises, or procedures to promote centralization to reduce symptoms in patients with acute low back pain with related (referred) lower extremity pain. Clinicians should consider using repeated exercises in a specific direction determined by treatment response to improve mobility and reduce symptoms in patients with acute, subacute, or chronic low back pain with mobility deficits. 
  • flexion exercises, combined with other interventions such as manual therapy, strengthening exercises, nerve mobilization procedures, and progressive walking, for reducing pain and disability in older patients with chronic low back pain with radiating pain.
  • utilizing lower-quarter nerve mobilization procedures to reduce pain and disability in patients with subacute and chronic low back pain and radiating pain.
  • moderate- to high-intensity exercise for patients with chronic low back pain without generalized pain
  • incorporating progressive, low-intensity, submaximal fitness and endurance activities into the pain management and health promotion strategies for patients with chronic low back pain with generalized pain.

Manual Therapy

Manual Therapy refers to spinal manipulation (a low-amplitude, high-velocity movement at the limit of joint range that takes the joint beyond the passive range of movement), spinal mobilisation (joint movement within the normal range of motion) and massage (manual manipulation or mobilisation of soft tissues).

The recommendations regarding spinal manipulation continue to show some variation and systematic reviews have demonstrated marginal treatment effects across heterogeneous groups of patients with low back pain[9][10]. In some guidelines manipulation is recommended, or presented as a therapeutic option, usually for short-term benefit, but others do not recommend it[3].  The reason for these differences is probably that the underlying evidence is not strong enough to result in similar recommendations regarding manipulation across all guidelines, leaving more room for interpretation.  There may also be local and political reasons involved.  Recent research has demonstrated that spinal manipulative therapy is effective for subgroups of patients and as a component of a comprehensive treatment plan, rather than in isolation[4]. Clinical prediction rules can be used to identify patients that will benefit form thrust manipulation[11][12][13][14].

The NICE guidelines recommend offering a course of manual therapy, including spinal manipulation, comprising up to a maximum of nine sessions over a period of up to 12 weeks in early management of non-specific LBP[1].  

Delitto et al[4] suggest that clinicians should consider utilising thrust manipulative procedures to reduce pain and disability in patients with mobility deficits and acute low back and back-related buttock or thigh pain.  Thrust manipulative and nonthrust mobilization procedures can also be used to improve spine and hip mobility and reduce pain and disability in patients with subacute and chronic low back and back-related lower extremity pain.

Traction

There is conflicting evidence for the efficacy of intermittent lumbar traction for patients with low back pain. There is preliminary evidence that a subgroup of patients with signs of nerve root compression along with peripheralization of symptoms or a positive crossed straight leg raise will benefit from intermittent lumbar traction in the prone position. There is moderate evidence that clinicians should not utilize intermittent or static lumbar traction for reducing symptoms in patients with acute or subacute, nonradicular low back pain or patients with chronic low back pain[4][15] and recent guidelines advise against traction as a treatment option[8].

Electrotherapy

Evidence for efficacy of most electrotherapy modalities in the managment of low back pain is weak or lacking[16][17].  Guidelines suggest that electrotherapy modalities (laser, interferrential, ultrasound, TENS) are not appropriate for non-specific low back pain[3][1]  Passive treatment modalities (for example bed rest, massage, ultrasound, electrotherapy, laser and traction) should be avoided as mono-therapy and not routinely be used, because they may increase the risk of illness behaviour and chronicity[18].

Cognitive Behavioural Therapy

Behavioral education, also known as cognitive behavioral theory, encompasses many aspects of patient education and counseling for patients with low back pain, including:

  • Activity pacing
  • Attention diversion
  • Cognitive restructuring
  • Goal setting
  • Graded exposure
  • Motivational enhancement therapy
  • Maintenance strategies
  • Problem-solving strategies

Henschke et al[19] in a recent Cochrane review, concluded there is moderate-quality evidence that operant therapy and behavioral therapy are more effective than waiting-list or usual care for short-term pain relief in patients with chronic low back pain, but no specific type of behavioral therapy is superior to another. In the intermediate to long term, there is no established difference between behavioral therapy and group exercise for management of pain or depressive symptoms in patients with chronic low back pain.

The NICE guidelines[1] suggest referral for a combined physical and psychological treatment programme that includes a cognitive behavioural approach and exercise, comprising around 100 hours over a maximum of 8 weeks, for people who have received at least one less intensive treatment and have high disability and/or significant psychological distress.

References

  1. ↑ 1.01.11.21.31.41.5 National Institute for Health and Care Excellence. ↑ Hill J, D Whitehurst, Lewis M, Bryan S, Dunn K, Foster N, Konstantinou, Main C, Mason E, Somerville S, Sowden G, Vohora K, Hay E. A randomised controlled trial and economic evaluation of stratified primary care management for low back pain compared with current best practice: The STarT Back trial.The Lancet, Volume 378, Issue 9802, Pages 1560 – 1571, 29 October 2011
  2. ↑ 3.03.13.23.33.4 Koes BW, van Tulder M, Lin C-WC, Macedo LG, McAuley J, Maher C. ↑ 4.04.14.24.34.4 Anthony Delitto, Steven Z. George, Linda Van Dillen, Julie M. Whitman, Gwendolyn Sowa, Paul Shekelle, Thomas R. Denninger, Joseph J. Godges. Low Back Pain: Clinical Practice Guidelines Linked to the International Classification of Functioning, Disability, and Health from the Orthopaedic Section of the American Physical Therapy Association. Journal of Orthopaedic and Sports Physical Therapy, 2012, 42(4)
  3. ↑ Stochkendahl MJ, Kjaer P, Hartvigsen J, et al. National Clinical Guidelines for non-surgical treatment of patients with recent onset low back pain or lumbar radiculopathy. Eur Spine J 2018; 27: 60-75.
  4. ↑ Van Wambeke P, Desomer A, Ailliet L, et al. Summary: ↑ Qaseem A, Wilt TJ, McLean RM, et al. Noninvasive treatments for acute, subacute, and chronic low back pain: a clinical practice guideline from the American College of Physicians. Ann Intern Med 2017; 166: 514-530.
  5. ↑ 8.08.1 Almeida M, Saragiotto B, Richards B, Maher C. Primary care management of non-specific low back pain: key messages from recent clinical guidelines. Med J Aust 2018; 208 (6): 272-275
  6. ↑ Assendelft WJ, Morton SC, Yu EI, Suttorp MJ, hekelle PG. Spinal manipulative therapy for low back pain. Cochrane Database Syst Rev. 2004;CD000447.
  7. ↑ Assendelft WJ, Morton SC, Yu EI, Suttorp MJ, Shekelle PG. Spinal manipulative therapy for low back pain. A meta-analysis of effectiveness relative to other therapies. Ann Intern Med. 2003;138:871-881
  8. ↑ Flynn T, Fritz J, Whitman J, et al. A clinical prediction rule for classifying patients with low back pain who demonstrate short-term improvement with spinal manipulation. Spine (Phila Pa 1976).
  9. ↑ Childs JD, Fritz JM, Flynn TW, et al. A clinical prediction rule to identify patients with low back pain most likely to benefit from spinal manipulation: a validation study. Ann Intern Med. 2004;141:920-928.
  10. ↑ Cleland JA, Fritz JM, Kulig K, et al. Comparison of the effectiveness of three manual physical therapy techniques in a subgroup of patients with low back pain who satisfy a clinical prediction rule: a randomized clinical trial. Spine (Phila Pa 1976).
  11. ↑ Hancock MJ, Maher CG, Latimer J, Herbert RD, McAuley JH. Independent evaluation of a clinical prediction rule for spinal manipulative therapy: a randomised controlled trial. Eur Spine J. 2008;17:936-943.
  12. ↑ Delitto A, Erhard RE, Bowling RW. ↑ Matthew S Thiese, Matthew Hughes and Jeremy Biggs. Electrical stimulation for chronic non-specific lowfckLRback pain in a working-age population: a 12-weekfckLRdouble blinded randomized controlled trial. BMC Musculoskeletal Disorders 2013, 14:117
  13. ↑ GE Bekkering, HJM Hendriks, BW Koes, RAB Oostendorp, RWJG Ostelo, JMC Thomassen, MW van Tulder. ↑ van Tulder M, Becker A, Bekkering T, Breen A, del Real MT, Hutchinson A, Koes B, Laerum E, Malmivaara A; COST B13 Working Group on Guidelines for the Management of Acute Low Back Pain in Primary Care. Chapter 3. ↑ Henschke N, Ostelo RW, van Tulder MW, et al. Behavioural treatment for chronic low-back pain. Cochrane Database Syst Rev. 2010;CD002014

Conteúdos relacionados

Fratura do Carrasco: Definição, Mecanismo e Tratamento

Fratura do Carrasco: Definição, Mecanismo e Tratamento

Definition/Description

Hangman’s fracture is a fracture of the axis in the cervical region. It is often seen with people who try to hang themselves but also occurs in sports or traffic accidents. The fracture is in most cases lethal. The fracture is caused by an extreme force on the upper vertebrae and especially on the dens of the axis. The fracture causes damage to the spinal cord which leads to paralysis of respiratory muscles and most often death1 .

Clinically Relevant Anatomy[1]

Axis - C2

A hangman’s fracture is the result of hyperextension of the upper cervical spine. The pedicles of the axis break symmetrically and the fracture may extend across the posterior part of the body. In contrary to what everyone thinks, the dens of C2 always remains intact. The pedicles are the smallest parts of the bony ring of the axis. They are additional weakened by the foramen transversarium on each side. There is no other cervical bony injury with a Hangman’s fracture.

Other tissues that may be damaged are the anterior ligament and the disc below the axis, both may be disrupted. Neurological injuries are rare because the spinal canal is sufficiently wide at this level.

Mechanism of Injury / Pathological Process

The mechanism of injury is a forced hyperextension of the head with distraction of the neck. This occurs when the nose is placed under the subjects chin with a hanging. Hangman’s fractures also occur in car accidents when an unrestrained passenger or driver strikes the dashboard or when rebound hyperextension en distraction of the neck.

Another mechanism of injury is a sudden forceful hyperextension centered on the chin. This mechanism of injury also occur in contact sports, diving or when falling[2].

Clinical Presentation

Usually the patient has non-specific complaints of suboccipital pain. Sometimes there is a clear spasm of the neck muscles. Patients may manifest neurological deficits, depending on the severity of vertebral displacement and the presence of other cervical spine fractures[3].

Diagnostic Procedures

The diagnosis of a hangman’s fracture can be made using x- rays and CT scans to see if there is a fracture of C2. To determine if there is ligamentous and/or soft tissue injury a MRI can be done. There are several grading systems for hangman’s fractures like Effendi[4], Francis and the Levine and Edwards[5] system.
The most commen used system to grade a Hangman fracture is the grading system of Effendi et al, later revised by Edwards and Levine. The classification systems of Levine and Edwards:[5]

  1. Type I: Caused by axial loading and hyperextension. There is less than 3mm subluxation of C2 on C3 and no angulation. This fracture is stable because the anterior longitudinal ligament and posterior longitudinal ligaments are intact along with the C2/C3 disk.
  2. Type II: Caused by axial loading and hyperextension followed by a rebound flexion and axial loading. There is subluxation of C2 on C3 greater than 4mm or 11° angulation. There is some damage to the anterior longitudinal ligament and significant structural damage to the posterior longitudinal ligament and C2/C3 disk. This fracture is unstable.
  3. Type IIA: Caused by flexion with distraction. These have no anterior displacement, but there is a severe angulation. The C2/C3 disk is damaged along with the posterior longitudinal ligaments. This fracture is unstable
  4. Type III: Caused by initial flexion and rebound extension with axial compression. There is severe displacement and angulation. The injury is accompanied by C2/C3 disk dislocation and unilateral or bilateral C2/C3 facet dislocation. There is also injury of the anterior and posterior longitudinal ligament. This fracture is considered unstable.

X-ray of the cervical spine with a Hangman’s fracture. Left without, right with annotation. C2 (outlined in red) is moved forward with respect to C3 (outlined in blue).

Outcome Measures

The healing rate can be evaluated by radiological appearance. The same system of Levine-Edwards is used for evaluating. Type I hangman’s fracture has a healing rate of almost 100%. The healing rate drops as the fracture becomes more unstable[5]. The ‘Neck Disability Index (NDI)’ can be used to evaluate the effects of treatment[6].

Management / Interventions

Treatment options are usually based on the stability of the hangman’s fracture. But most publications advocate that the primary treatment should be conservative.[5]

Surgical interventions are usually performed in unstable fractures or when there is a possible risk of later instability. Type IIa and III fractures with significant dislocation are almost always treated surgically[5].

The physiotherapeutic intervention is a conservative treatment consisting of a period of traction and external immobilization. The external immobilization can be rigid or nonrigid depending on the type of fracture. The conservative treatment has more chance of being effective for stable and neurologically normal patients.
Effendi type I, II and Levine-Edwards type II fractures can be treated with nonrigid immobilization alone. Type IIa and III Levine-Edwards fractures are to be treated with rigid immobilization and traction[5].
The use of the immobilization brace (Halo-Vest) should be well considered and explained to the patient. A recent publication reported a 39,1% failure rate and 60,9% chance on complications[7]

Since literature is scare the optimal treatment is not yet clear.

Differential Diagnosis

The only differential diagnosis to consider is chronic spondylolisthesis of the axis. This is a rare disorder associated with congenital abnormalities of the cervical spine[8]

References

  1. ↑ T.G. Williams. Hangman’s Fracture. The journal of bone and Joint surgery, pp. 82-89
  2. ↑ Yilmaz, F., Akbulut, A. & Kose, O. (2010). An unusual presentation of an atypical hangman’s fracture. J Emerg Trauma Shock, 3(3), pp. 292–293.
  3. ↑ Pathria, M.N. Physical injury: Spine. In: Resnick D, ed. Diagnosis of Bone and Joint Disorders. W.B. Saunders Co.; 2002; 2964-2967
  4. ↑ Effendi, B., Roy, D., Cornish B, Dussault, R.G. & Laurin, C.A. (1981). Fractures of the ring of the axis: a classification based on analysis or 131 cases. J Bone Joint Surg Br, 63, pp. 319–27.
  5. ↑ 5.05.15.25.35.45.5 Li, X., Dai, L., Lu, H. & Chen X. (2006). A systematic review of the management of hangman’s fractures. European Spine Journal, 15(3), pp. 257-269.
  6. ↑ Vernon, H. & Mior, S. (1991). The Neck Disability Index: a study of reliability an validity. Journal of Manipulative and Physiological Therapeutics, 14(7), pp. 409-415.
  7. ↑ Shin, J.J., Kim, S.J., Kim, T.H., Shin, H.S., Hwang, Y.S. & Park, S.K. (2010). Optimal use of the halo-vest orthosis for upper cercival spine injuries. Yonsei Medical Journal, 51(5), pp. 648-652.
  8. ↑ Pathria, M.N. Physical injury: Spine. In: Resnick D, ed. Diagnosis of Bone and Joint Disorders. W.B. Saunders Co.; 2002; 2964-2967.

Conteúdos relacionados

Tratamento com ondas de choque

Tratamento com ondas de choque

Tratamento com ondas de choque pode atenuar sintomas do “ombro congelado”, causado pelo diabetes:

Nos casos de “ombro congelado” em pacientes com diabetes, o tratamento extracorpóreo por ondas de choque pode ser um recurso terapêutico mais seguro do que as injeções de esteroides ou a cirurgia, de acordo com os resultados preliminares de uma pesquisa.

Os resultados de um pequeno estudo observacional não controlado foram publicados on-line em 29 de novembro no periódico Diabetes Care, pela Dra. Flavia Santoboni, psicóloga da Sapienza Università di Roma, na Itália, e colaboradores.

A capsulite adesiva, popularmente conhecida como “ombro congelado”, se caracteriza por dores fortes no ombro com limitação progressiva da mobilidade articular e incapacidade funcional. É o distúrbio musculoesquelético mais comum dos membros superiores entre diabéticos.

O tratamento do “ombro congelado” é feito com fisioterapia, administração de esteroides por via oral ou por injeções intra-articulares, terapia extracorpórea por ondas de choque e liberação capsular por artroscopia.

Tratamento com ondas de choque

Nos pacientes diabéticos, a duração do benefício dos esteroides pode ser mais curta e pode aumentar significativamente a glicemia. “Portanto, seria preferível evitar os esteroides e optar por terapias alternativas nesses indivíduos”, afirmaram os autores.

———-

Esta gostando deste post sobre “Tratamento com ondas de choque” então confira também nosso Curso de Ondas de Choque:

CURSO ONDAS DE CHOQUE

———-

O tratamento com ondas de choque pode ser alternativa aos esteroides para diabéticos com capsulite adesiva

O novo estudo — que acredita-se ser o primeiro a avaliar o tratamento extracorpóreo por ondas de choque nos desfechos funcionais de pacientes diabéticos com capsulite adesiva — recrutou 50 pacientes consecutivos (sete com diabetes tipo 1 e 43 com diabetes tipo 2), com média global da duração da dor decorrente da capsulite adesiva de 15,7 meses.

Os critérios de inclusão foram: diagnóstico de diabetes, dor no ombro, perda da amplitude do movimento em duas ou mais direções (abdução, flexão, rotação externa e rotação interna) > 75% durante pelo menos três meses e ausência de tratamento além de analgésicos nos últimos três meses.

Todos os pacientes receberam tratamento extracorpóreo por ondas de choque uma vez por semana ao longo de três semanas, com 2.400 pulsos no sentido anteroposterior na articulação anterior do ombro, usando uma densidade de fluxo de energia baixa/moderada (0,06 a 0,14 mJ/mm2, dependendo da tolerância individual à dor).

A melhora funcional foi importante, iniciando aos dois meses de tratamento, com melhora adicional aos quatro e aos seis meses. Esta melhora se traduziu na diminuição geral de 3,14 vezes da pontuação na Escala Visual Analógica, redução de 2,97 vezes da pontuação no Disabilities of the Arm, Shoulder, and Hand Score Questionnaire e aumento de 39,7% da pontuação do Constant Shoulder Score.

Não foram informados efeitos colaterais relevantes ao longo do estudo.

“Os resultados indicam que o tratamento extracorpóreo por ondas de choque pode ser eficaz, viável e bem tolerado, podendo, portanto, representar uma alternativa viável aos esteroides para o tratamento da capsulite adesiva em pacientes diabéticos”, afirmaram os autores.

No entanto, destacaram eles, “esses resultados precisam ser confirmados por um estudo randomizado controlado”.

Dra. Flavia Santoboni e colaboradores declaram não possuir conflitos de interesses relevantes ao tema.

Confira aqui o artigo completo (Tratamento com ondas de choque) em inglês – ARTIGO COMPLETO

———-

Gostou deste post sobre Tratamento com ondas de choque, então clique abaixo e confira nosso CURSO DE ONDAS DE CHOQUE – Curso com 10 horas/aula sendo teórico e prático. Os alunos saem aptos a aplicar a técnica. Incluso apostila colorida de fácil entendimento e certificado de conclusão.

CURSO ONDAS DE CHOQUE

Conteúdos relacionados

Complicações e Diagnostico da Fascite Plantar

Complicações e Diagnostico da Fascite Plantar

Em casos raros, a fáscia plantar pode se romper espontaneamente. O risco de tal ruptura é grandemente aumentado por uma história de tratamento com injeção de corticosteróide. [ 28 ] As seqüelas de ruptura a longo prazo ocorrem em aproximadamente 50% dos pacientes que apresentam uma ruptura da fáscia plantar. [ 28 , 29 ] Além disso, a tensão do arco longitudinal responde por mais de 50% das complicações crônicas da ruptura da fascia plantar. [ 28 , 29 ]

A injeção de corticosteróide na almofada de gordura superficial pode causar a necrose da almofada gorda, devido à perda da absorção de choque normalmente fornecida pela almofada de gordura superficial, com dor subsequente durante a fase inicial da fase de postura com a ambulação. Este desenvolvimento poderia criar uma deficiência significativa no caso de um caso de compensação do trabalhador.

As possíveis complicações incluem o achatamento do arco longitudinal e hipoestesia do calcanhar, bem como as possíveis complicações associadas à ruptura da fascia plantar. A tensão do arco longitudinal parece representar mais de 50% das complicações crônicas. [ 28 , 29 ]


Conteúdos relacionados

A fáscia plantar é uma estrutura fibrosa espessa que se estende do calcâneo até a base dos dedos, desempenhando um papel crucial na manutenção do arco longitudinal do pé e na absorção de impacto durante a marcha. Quando ocorre uma ruptura, seja espontânea ou traumática, as consequências podem ser significativas. A ruptura espontânea é rara, mas o risco aumenta consideravelmente em pacientes que receberam injeções de corticosteroides, que podem enfraquecer o tecido fascial. Estudos indicam que cerca de 50% dos pacientes com ruptura da fáscia plantar desenvolvem sequelas a longo prazo, como dor crônica e deformidades. A tensão excessiva no arco longitudinal é um fator que contribui para mais da metade dessas complicações crônicas, podendo levar a alterações biomecânicas que afetam a marcha e a postura.

Além disso, a injeção de corticosteroides na almofada de gordura superficial do calcanhar pode causar necrose dessa estrutura, resultando em perda da capacidade de absorção de choque. Isso pode gerar dor intensa durante a fase de apoio da marcha, especialmente no início do contato com o solo. Em casos de compensação trabalhista, essa condição pode representar uma deficiência significativa, impactando a capacidade funcional e a qualidade de vida do paciente. Outras complicações incluem o achatamento do arco longitudinal e a hipoestesia do calcanhar, que podem estar associadas a danos neurológicos ou mecânicos. O diagnóstico precoce e o manejo adequado são essenciais para minimizar os riscos e melhorar o prognóstico.

Indicações para a Auriculoterapia

Indicações para a Auriculoterapia

Indicações para a Auriculoterapia

A auriculoterapia é uma técnica terapêutica que pode ser usada de forma independente e complementar de qualquer outro tratamento. Esta técnica é muitas vezes referida como acupuntura de ouvido ou acupuntura auricular e consiste em tratar pontos muito precisos na orelha para fins terapêuticos. A auriculoterapia pode ser um ativo real onde o tratamento convencional não possui eficiência ou não pode ser usado mais por causa de efeitos colaterais sérios.

Indicações para a Auriculoterapia

Indicações para a auriculoterapia são inúmeras e cobre quase todas as disciplinas da medicina moderna:

Dor: dores de cabeça, enxaqueca, dor de dente, neuralgia do trigemino, dor nas costas, dor resultante da cirurgia, zona, artrite, fibromialgia, reuma, dor estomacal, dores relacionadas ao esporte

Digestão: problemas do estômago e do intestino como gastrite, refluxo, síndrome do intestino irritável, doença de Crohn, colite ulcerosa, hemorróidas, …

Indicações psicossomáticas: estresse, ansiedade, problemas de sono, fadiga crônica, irregularidades do ritmo cardíaco

Vias aéreas: sinisite, febre dos fenos, otite, rinite, asma, …

ENT: zumbido, vertigem, boca seca, problemas de deglutição, …

Neurologia: nevralgia, enxaqueca, zona, análise facial, conseqüências de CVA, queixas ansiodepressivas, sono

Problemas hormonais: problemas na menopausa, (pré) problemas menstruais, fertilidade, queixas durante a gravidez e parto 

Boca: dor no dente, problemas envolvendo articulação temporomandibular, …

Desintoxicações: tabac

Oncologia: conseqüências do câncer e seu tratamento como dor, nevralgia, problemas gastrointestinais, …

———-

Esta gostando deste post sobre Indicações para a Auriculoterapia ? Veja tambem outras informações sobre a auriculoterapia:

CURSO DE AURICULOTERAPIA

Acupuntura Estetica Facial

Introdução Sobre Acupuntura Estética Facial

VOCÊ SABIA DISSO…?

  • Você sabia que Hipócrates já usava auriculoterapia para tratar a impotência?
  • Você sabia que muitas belas mulheres egípcias tinham seus ouvidos tratados em pontos bem definidos para evitar a gravidez?
  • Você sabia que na China antiga, a auriculoterapia foi usada para tratar sintomas e conseqüências da hepatite?
  • Você sabia que na Turquia antiga, a auriculoterapia era usada cauterizando certos pontos da orelha?

Confira esse artigo completo para DOWNLOAD

Auriculoterapia Chinesa para melhoria de qualidade de vida de equipe de Enfermagem

Kurebayashi, Leonice Fumiko Sato; Silva, Maria Júlia Paes da.
Rev Bras Enferm; 68(1): 117-123, Jan-Feb/2015. tab, graf
Artigo em Português | LILACS | ID: lil-744606

Resumo

Objetivo: avaliar a efi cácia da auriculoterapia para melhoria de qualidade de vida e redução de estresse em equipe de Enfermagem. Método: ensaio clínico randomizados 175 sujeitos em Controle (G1), Grupo Protocolo(G2) e sem Protocolo(G3). Foram avaliados pela Lista de Sintomas de Stress e SF36v2 no início, após 12 sessões e follow up (30 dias), entre janeiro/julho de 2012. Resultados: os dois grupos de intervenção reduziram o estresse (p<0.05), com efeito superior para o G3 (d=1,15). O G3 também foi superior na melhoria de qualidade de vida, especialmente no domínio físico (p=0.05). Conclusão: a auriculoterapia individualizada (G3) foi superior em efeito do que a auriculoterapia com protocolo (G2) para redução de estresse e melhoria de qualidade de vida.

Gostou deste post sobre Indicações para a Auriculoterapia ? Então confira também nosso Curso de Auriculoterapia que é teórico e prático e os alunos saem aptos a aplicar a técnica com ministrante de grande experiência na área !!
Outras informações:
campcursos@campcursos.com.br
WhatsApp (19) 99677-8054
Fone (19) 3091-0353

Conteúdos relacionados