Chronic Obstructive Pulmonary Disease (COPD) is a non-reversible progressive disease that is characterised by symptoms such as shortness of breath, wheezing and a cough that produces a high volume of secretions. It may include Asthma, Emphysema and bronchitis,
Clinically Relevant Anatomy
See this page for information on the anatomy of the lungs
Causes
Smoking – The primary risk factor for COPD is chronic tobacco smoking. In the United States, 80 to 90% of cases of COPD are due to smoking.[1]
Occupational exposure – Intense and prolonged exposure to workplace dusts found in coal mining, gold mining, and the cotton textile industry and chemicals such as cadmium, isocyanates, and fumes from welding have been implicated in the development of airflow obstruction, even in nonsmokers.[2] Workers who smoke and are exposed to these particles and gases are even more likely to develop COPD. Intense silica dust exposure causes silicosis, a restrictive lung disease distinct from COPD; however, less intense silica dust exposures have been linked to a COPD-like condition.[3] The effect of occupational pollutants on the lungs appears to be substantially less important than the effect of cigarette smoking.[4]
Air pollution – Studies in many countries have found that people who live in large cities have a higher rate of COPD compared to people who live in rural areas.[[5] Urban air pollution may be a contributing factor for COPD as it is thought to slow the normal growth of the lungs although the long-term research needed to confirm the link has not been done. In many developing countries indoor air pollution from cooking fire smoke (often using biomass fuels such as wood and animal dung) is a common cause of COPD, especially in women.[6]
Genetics – Some factor in addition to heavy smoke exposure is required for a person to develop COPD. This factor is probably a genetic susceptibility. COPD is more common among relatives of COPD patients who smoke than unrelated smokers.[7]] The genetic differences that make some peoples’ lungs susceptible to the effects of tobacco smoke are mostly unknown
Autoimmune disease – There is mounting evidence that there may be an autoimmune component to COPD.[8] Many individuals with COPD who have stopped smoking have active inflammation in the lungs.[9]The disease may continue to get worse for many years after stopping smoking due to this ongoing inflammation.[9] This sustained inflammation is thought to be mediated by autoantibodies and autoreactive T cells.[10]
Mechanism of Injury / Pathological Process
It is not fully understood how tobacco smoke and other inhaled particles damage the lungs to cause COPD. The most important processes causing lung damage are:
Oxidative stress produced by the high concentrations of free radicals in tobacco smoke.
Cytokine release due to inflammation as the body responds to irritant particles such as tobacco smoke in the airway.
Tobacco smoke and free radicals impair the activity of antiprotease enzymes such as alpha 1-antitrypsin, allowing protease enzymes to damage the lung.
Clinical Presentation
COPD is a complex interaction between Chronic Bronchitis, Emphysema, and Asthma
Asthma
Asthma is a chronic lung disease which is a very common respiratory condition. It is also known as a reactive airway disease which is inconvenient most of the time but manageable. Asthma is caused by inflammation and constriction of bronchial walls which leads to a series of spasmodic attacks of wheezing and shortness of breath as a result of the hyper-reactivity of smooth muscle in the bronchial walls and in the absence of any other apparent cause. There are various factors such as exposure to cigarette smoke, climate change, physical exertion or emotional stress that causes asthma. It begins during childhood and the disease is commonly triggered by viral infection[11].
Asthma can be diagnosed by the presence of the signs and symptoms. The diagnosis is normally confirmed by presenting a response to a inhaled bronchodialator. Often pulmonary function tests, chest x-rays and blood tests can also be done in order to confirm the diagnosis.
Chronic bronchitis
Lung damage and inflammation in the large airways results in chronic bronchitis. Chronic bronchitis is defined in clinical terms as a cough with sputum production on most days for 3 months of a year, for 2 consecutive years.[12] In the airways of the lung, the hallmark of chronic bronchitis is an increased number (hyperplasia) and increased size (hypertrophy) of the goblet cells and mucous glands of the airway. As a result, there is more mucus than usual in the airways, contributing to the narrowing of the airways and causing a cough with sputum. Microscopically there is infiltration of the airway walls with inflammatory cells. Inflammation is followed by scarring and remodeling that thickens the walls and also results in narrowing of the airways. As chronic bronchitis progresses, there is squamous metaplasia (an abnormal change in the tissue lining the inside of the airway) and fibrosis (further thickening and scarring of the airway wall). The consequence of these changes is a limitation of airflow.[13]
Patients with advanced COPD that have primarily chronic bronchitis rather than emphysema were commonly referred to as “blue bloaters” because of the bluish color of the skin and lips (cyanosis) seen in them.[14] The hypoxia and fluid retention leads to them being called “Blue Bloaters.”
Emphysema
A lateral chest x-ray of a person with emphysema. Note the barrow chest and flap diaphragm.
Lung damage and inflammation of the alveoli results in emphysema. Emphysema is defined as enlargement of the air spaces distal to the terminal bronchioles, with destruction of their walls.[12] The destruction of air space walls reduces the surface area available for the exchange of oxygen and carbon dioxide during breathing. It also reduces the elasticity of the lung itself, which results in a loss of support for the airways that are embedded in the lung. These airways are more likely to collapse causing further limitation to airflow. The effort made by patients suffering from emphysema during exhalation, causes a pink color in their faces, hence the term commonly used to refer to them, “pink puffers”.
Diagnostic Procedures
Unfortunately there is no single diagnostic test for COPD; diagnosis relies on the presence/absence of symptoms and clinical judgement. The best approach is to undertake a detailed subjective history and physical examination. As COPD is not curable the earlier that it is diagnosed, the earlier treatment can start and that may help to slow down the progression of the disease and the subsequent damage to the lungs.
Assessment – A diagnosis of COPD should be considered in patients over the age of 35 who have a risk factor (generally smoking) and who present with exertional breathlessness, chronic cough, regular sputum production, frequent winter ‘bronchitis’ or wheeze.
Spirometry – The presence of airflow obstruction should be confirmed by performing post-bronchodilator spirometry. All health professionals involved in the care of people with COPD should have access to spirometry and be competent in the interpretation of the results
X-Ray – An x-ray of the chest may show an over-expanded lung (hyperinflation) and can be useful to help exclude other lung diseases.
Pulmonary function tests – Complete pulmonary function tests with measurements of lung volumes and gas transfer may also show hyperinflation and can discriminate between COPD with emphysema and COPD without emphysema.
Blood tests – A blood sample taken from an artery can be tested for blood gas levels which may show low oxygen levels (hypoxemia) and/or high carbon dioxide levels (respiratory acidosis). A blood sample taken from a vein may show a high blood count (reactive polycythemia), a reaction to long-term hypoxemia.
Poor lung function if a risk factor for all cause of cardiovascular mortality and poorer health[16]
Limitations being:
FEV1 measurements are based on an artificial manoeuvre and do not always correlate with clinically relevant outcomes such as dyspnoea, health status, exercise capacity, or exacerbations[17][18]
Patients with similar FEV1 may represent different underlying phenotypes.
Reference equations for lung function by European Community for Coal and Steel are disputed and limited in predicting lung function in the general population [19]
No minimal important difference (MID) has been established yet. It was suggested that an appropriate range of values for the MID for FEV1 might be 100-140 mL but the MID for FEV1 remains poorly defined for COPD [20]
Lung Volumes
Changes in absolute lung volumes can occur in COPD patients even in the absence of FEV1 changes. Progressive hyperinflation due to airflow limitation and loss of lung elastic recoil not only increases the work required during inspiration but also profoundly decreases the ventilatory reserve and increases the sense of effort and dyspnoea[21]
In terms of measurement static lung hyperinflation and its increase during exercise (dynamic hyperinflation) are measured as elevations of total lung capacity (TLC), functional residual capacity (FRC), residual volume (RV) and as a decrease in inspiratory capacity (IC)[15].
Strengths of lung volumes include:
Indices of dynamic hyperinflation correlate better than FEV1 with activity limitation and exertional dyspnoeaand pharmacological and surgical lung volume reduction have been associated with improvements in exercise performance and dyspnoea[22][23]
A severely reduced IC/TLC ratio with a threshold value of 25% has been shown to predict mortality in COPD patients[24]
Weaknesses include:
Body plethysmography remains the gold standard for the measurement of lung volumes such as TLC, FRC and RV. Spirometrically derived assessments of lung hyperinflation are more difficult to interpret in the absence of simultaneous bodyplethysmographic volume measurements to rule out a concomitant restrictive ventilatory disorder[25]
The reproducibility of FRC, IC and RV in absolute values has yet to be demonstrated. Measurement of IC alone is not a reliable marker of lung hyperinflation and does not consistently reflect changes in FRC or TLC[25]
The natural course of dynamic hyperinflation in COPD is unknown and seems likely to be highly variable among COPD patients [25]
Encouraging patients with COPD to stop smoking is one of the most important components of their management. All COPD patients still smoking, regardless of age, should be encouraged to stop, and offered help to do so, at every opportunity.
Exercise
Exercise prescription is a key component of pulmonary rehabilitation programmes, which are part of the non-pharmacological approach to managing COPD. There is a high level of evidence for the benefits of pulmonary rehabilitation for people with COPD[27] Strength and endurance exercise are endorsed for people with COPD.[28]
Muscles that are required for arm exercise are also involved in movement of the chest wall during respiration and thus the need to breathe often compromises the individual’s ability to undertake daily activities, therefore exercise prescription involving arm exercise needs to be carefully prescribed.[29]
Promote Effective Inhaled Therapy
In people with stable COPD who remain breathless or have exacerbations despite use of short-acting bronchodilators as required, offer the following as maintenance therapy:
if forced expiratory volume in 1 second (FEV1)≥50% predicted: either long-acting beta2 agonist (LABA) or long-acting muscarinic antagonist (LAMA)
if FEV1
Offer LAMA in addition to LABA + ICS to people with COPD who remain breathless or have exacerbations despite taking LABA + ICS, irrespective of their FEV1.
Provide Pulmonary Rehabilitation
Pulmonary rehabilitation should be made available to all appropriate people with COPD including those who have had a recent hospitalisation for an acute exacerbation.
Use Non-Invasive Ventilation
Non-invasive ventilation (NIV) should be used as the treatment of choice for persistent hypercapnicventilatory failure during exacerbations not responding to medical therapy. It should be delivered by staff trained in its application, experienced in its use and aware of its limitations. When patients are started on NIV, there should be a clear plan covering what to do in the event of deterioration and ceilings of therapy should be agreed.
Manage Exacerbations
The frequency of exacerbations should be reduced by appropriate use of inhaled corticosteroids and bronchodilators, and vaccinations.
The impact of exacerbations should be minimised by:
giving self-management advice on responding promptly to the symptoms of an exacerbation
starting appropriate treatment with oral steroids and/or antibiotics
use of non-invasive ventilation when indicated
use of hospital-at-home or assisted-discharge schemes
Ensure Multidisciplinary Working
COPD care should be delivered by a multidisciplinary team.
Managing Symptoms and Conditions in Stable COPD
Breathlessness and Exacerbations
Manage breathlessness and exercise limitation with inhaled therapy
For exacerbations or persistent breathlessness:
use long-acting bronchodilators or LABA + ICS
consider adding theophylline if still symptomatic
Offer pulmonary rehabilitation to all suitable people
Refer patients who are breathless, have a single large bulla on a CT scan and an FEV1 less than 50% predicted for consideration of bullectomy
Refer people with severe COPD for consideration of lung volume reduction surgery if they remain breathless with marked restrictions of their activities of daily living, despite maximal medical therapy (including rehabilitation), and meet all of the following:
FEV1 greater than 20% predicted
PaCO2 less than 7.3 kPa
upper lobe predominant emphysema
TLCO greater than 20% predicted
Consider referring people with severe COPD for assessment for lung transplantation if they remain breathless with marked restrictions of their activities of daily living despite maximal medical therapy. Considerations include:
age
FEV1
PaCO2
homogeneously distributed emphysema on CT scan
elevated pulmonary artery pressures with progressive deterioration
comorbidities
local surgical protocols
Frequent Exacerbations
Optimise inhaled therapy
Offer vaccinations and prophylaxis
Give self-management advice
Consider osteoporosis prophylaxis for people requiring frequent oral corticosteroids
Cor Pulmonale
Consider in people who have peripheral edema, a raised venous pressure, a systolic parasternal heave, a loud pulmonary second heart sound
Exclude other causes of peripheral edema
Perform pulse oximetry, ECG and echocardiogram if features of cor pulmonale
Assess need for LTOT
Treat edema with diuretic
Angiotensin-converting enzyme inhibitors, calcium channel blockers, alpha-blockers are not recommended
Digoxin may be used where there is atrial fibrillation
Respiratory Failure
Assess for appropriate oxygen
Consider referral for assessment for long-term domiciliary NIV therapy
Abnormal BMI
Refer for dietetic advice
Offer nutritional supplements if the BMI is low
Pay attention to weight changes in older patients (especially>3 kg)
Chronic Productive Cough
Consider mucolytic therapy
Anxiety and Depression
Alpha-1 Antitrypsin Deficiency
Offer referral to a specialist centre to discuss the clinical management of this condition
Alpha-1 antitrypsin replacement therapy is not recommended
Palliative Setting
Opioids should be used when appropriate for the palliation of breathlessness in people with end-stage COPD unresponsive to other medical therapy
Use benzodiazepines, tricyclic antidepressants, major tranquillisers and oxygen to treat breathlessness
Provide access to multidisciplinary palliative care teams and hospices
Resources
KNGF guidelines for physical therapy in patients with chronic obstructive pulmonary disease
Videos
References
↑Young RP, Hopkins RJ, Christmas T, Black PN, Metcalf P, Gamble GD (August 2009). “COPD prevalence is increased in lung cancer, independent of age, sex and smoking history”. Eur. Respir. J. 34 (2): 380–6
↑Devereux, Graham (May 2006). “ABC of chronic obstructive pulmonary disease. Definition, epidemiology, and risk factors”. BMJ 332 (7550): 1142–4
↑Hnizdo E, Vallyathan V (April 2003). “Chronic obstructive pulmonary disease due to occupational exposure to silica dust: a review of epidemiological and pathological evidence”. Occup Environ Med 60 (4): 237–43
↑Loscalzo, Joseph; Fauci, Anthony S.; Braunwald, Eugene; Dennis L. Kasper; Hauser, Stephen L; Longo, Dan L. (2008). Harrison’s Principles of Internal Medicine (17th ed.). McGraw-Hill Professional
↑Halbert RJ, Natoli JL, Gano A, Badamgarav E, Buist AS, Mannino DM (September 2006). “Global burden of COPD: systematic review and meta-analysis”. Eur. Respir. J. 28 (3): 523–32
↑Kennedy SM, Chambers R, Du W, Dimich-Ward H (December 2007). “Environmental and occupational exposures: do they affect chronic obstructive pulmonary disease differently in women and men?”. Proceedings of the American Thoracic Society 4 (8): 692–4.
↑ilverman EK, Chapman HA, Drazen JM, et al. (June 1998). “Genetic epidemiology of severe, early-onset chronic obstructive pulmonary disease. Risk to relatives for airflow obstruction and chronic bronchitis”. Am. J. Respir. Crit. Care Med. 157 (6 Pt 1): 1770–8
↑Agustí A, MacNee W, Donaldson K, Cosio M. (2003). “Hypothesis: does COPD have an autoimmune component?”. Thorax 58 (10): 832–4
↑ 9.09.1Rutgers, Steven R.; Postma, Dirkje S.; Ten Hacken, Nick H. .T.; Kauffman, Henk F.;van der Mark,Thomas W; Koeter, Gerard H.; Timens, Wim (2000). “Ongoing airway inflammation in patients with COPD who do not currently smoke”. Thorax 55 (1): 12–18.
↑Feghali-Bostwick CA, Gadgil AS, Otterbein LE, et al. (January 2008). “Autoantibodies in patients with chronic obstructive pulmonary disease”. Am. J. Respir. Crit. Care Med. 177 (2): 156–63. doi:10.1164/rccm.200701-014OC
↑ 12.012.1Longmore, J. M.; Murray Longmore; Wilkinson, Ian; Supraj R. Rajagopalan (2004). Oxford handbook of clinical medicine. Oxford [Oxfordshire]: Oxford University Press. pp. 188–9. ISBN 0-19-852558-3
↑Kumar P, Clark M (2005). Clinical Medicine (6th ed.). Elsevier Saunders. pp. 900–1. ISBN 0702027634
↑Chung C, Delaney J, Hodgins R (2008). “Respirology”. in Somogyi, Ron; Colman, Rebecca. The Toronto notes 2008: a comprehensive medical reference and review for the Medical Council of Canada Qualifying Exam – Part 1 and the United States Medical Licensing Exam – Step 2. Toronto: Toronto Notes for Medical Students. p. R9. ISBN 0-9685928-8-0
↑ 15.015.1Glaab T. Vogelmeier C and Buhl R. Outcome measures in chronic obstructive pulmonary disease (COPD): strengths and limitations. Respiratory Research. 2010:11:79
↑Sin DD, Wu L, Man SF: The relationship between reduced lung function and cardiovascular mortality: a population-based study and a systematic review of the literature. Chest 2005, 127:1952-1959
↑Cazzola M, MacNee W, Martinez FJ, Rabe KF, Franciosi LG, Barnes PJ, Brusasco V, Burge PS, Calverley PMA, Celli BR, Jones PW, Mahler DA, Make B, Miravitlles M, Page CP, Palange P, Parr D, Pistolesi M, Rennard SI, Rutten-van Mölken MP, Stockley R, Sullivan SD, Wedzicha JA, Wouters EF, American Thoracic Society/European Respiratory Society Task Force on outcomes of COPD: Outcomes for COPD pharmacological trials: from lung function to biomarkers. Eur Respir J 2008, 31:416-469
↑11.Wise RA: The value of forced expiratory volume in 1 second decline in the assessment of chronic obstructive pulmonary disease progression. Am J Med 2006, 119:4-11
↑12.Pellegrino R, Viegi G, Brusasco V, Crapo RO, Burgos F, Casaburi R, Coates A, van der Grinten CPM, Gustafsson P, Hankinson J, Jensen R, Johnson DC, MacIntyre N, McKay R, Miller MR, Navajas D, Pedersen OF, Wanger J: Interpretative strategies for lung function tests. Eur Respir J 2005, 26:948-968
↑4.Cazzola M, MacNee W, Martinez FJ, Rabe KF, Franciosi LG, Barnes PJ, Brusasco V, Burge PS, Calverley PMA, Celli BR, Jones PW, Mahler DA, Make B, Miravitlles M, Page CP, Palange P, Parr D, Pistolesi M, Rennard SI, Rutten-van Mölken MP, Stockley R, Sullivan SD, Wedzicha JA, Wouters EF, American Thoracic Society/European Respiratory Society Task Force on outcomes of COPD: Outcomes for COPD pharmacological trials: from lung function to biomarkers. Eur Respir J 2008, 31:416-469
↑O’Donnell DE, Laveneziana P: Physiology and consequences of lung hyperinflation in COPD. Eur Respir Rev 2006, 15:61-67
↑17.O’Donnell DE: Is sustained pharmacologic lung volume reduction now possible in COPD? Chest 2006, 129:501-503
↑18.Criner GJ, Belt P, Sternberg AL, Mosenifar Z, Make BJ, Utz JP, Sciurba F: National Emphysema Treatment Trial Research Group. Effects of lung volume reduction surgery on gas exchange and breathing pattern during maximum exercise. Chest 2009, 135:1268-79
↑19.Casanova C, Cote C, de Torres JP, Aguirre-Jaime A, Marin JM, Pinto-Plata V, Celli BR: Inspiratory-to-total lung capacity predicts mortality in patients with chronic obstructive pulmonary disease. Am J Respir Crit Care Med 2005, 171:591-597
↑ 25.025.125.2O’Donnell DE, Laveneziana P: Physiology and consequences of lung hyperinflation in COPD. Eur Respir Rev 2006, 15:61-67
↑Roisin RR, Rabe KF, Anzueto A, et al. Global strategy for the diagnosis management, and prevention of chronic obstructive pulmonary disease. Bethesda, MD: Global Initiative for Chronic Obstructive Lung Disease, 2008; 1–91.
↑Skinner, Margot. Strength and endurance exercise endorsed for people with COPD. Physical Therapy Reviews, Volume 14, Number 6, December 2009 , pp. 418-418(1)
↑Ennis S, Alison J, McKeough Z. The effects of arm endurance and strength training on arm exercise capacity in people with chronic obstructive pulmonary disease. Phys Ther Rev 2009;14(4):226–39.
↑National Institute for Health and Clinical Excellence. Chronic obstructive pulmonary disease: Management of chronic obstructive pulmonary disease in adults in primary and secondary care. Available from http://guidance.nice.org.uk/CG91 [last accessed 2/8/10]
Strength training is a type of physical exercise specializing in the use of resistance to induce muscular contraction which builds the strength, anaerobic endurance, and size of skeletal muscles. It is also known as resistance training and it is indicated for muscle hypertrophy, strength gain, sport performance and physical rehabilitation, but in the last few years it has been promoted as a means for health promotion and disease prevention[1][2].
Benefits of strength training
When properly performed, strength training can provide significant functional benefits and improvement in overall health and well-being, including increased bone, muscle, tendon, and ligament strength and toughness, improved joint function, reduced potential for injury, increased bone density, increased metabolism, increased fitness and improved cardiac function. Training commonly uses the technique of progressively increasing the force output of the muscle through incremental weight increases and uses a variety of exercises and types of equipment to target specific muscle groups.
Principles of strength training
DeLorme Principle: it is a method of exercise with weights for the purpose of strengthening muscles in which sets of repetitions are repeated with rests between sets. The technique involves isotonic exercise and determination of the maximum level of resistance. Thomas DeLorme’s work in the 1940 s proposes a progressive resistance exercise (PRE) program based on 10 repetitions maximum (10RM) where subject begins sets of training by performing the first set of 10 at 50% 10RM, the second at 75% 10RM and the third (final) at 100% of the 10RM[3].
Oxford Principle: In opposite was created the ‘Oxford Technique’ as a regressive loading in each set in which the full (100%) 10RM was the first set and subsequent two sets were reduced to 75% and to 50% of the 10RM[3].
Repetition Maximum:which is often expressed as 1RM, or one-repetition maximum indicates the heaviest weight that can be lifted with maximum effort in a single repetition
10 Repetition Maximum or 10 RM: is the maximum weight that a subject can lift 10 times, In PRE, 10RM of a subject is determined
Comparison between the DeLorme and Oxford principles
Apparently, a sparse number of research studies have directly compared these two resistance training (RT) methods. Interestingly in one such comparison, Fish et al.[4] reported no significant differences between both RT methods on strength gains. A study was conducted by da Silva et al. (2010) to compare the two principles of strength training and it was concluded from the results that there were no significant differences between the DeLorme or Oxford methods of RT on muscle performance or on serum enzymes activity responses over a 4 week period of training. Each method of training resulted in significant, but comparable, muscle strength gains and a low risk of injury. Thus the choice of one or another of these RT methods is acceptable for moderately active men.[3]
↑Kraemer W.J., Ratamess N.A. Fundamentals of resistance training: progression and exercise prescription. Med. Sci. Sports Exerc. 2004;36:674-688.
↑ACSM American College of Sports Medicine position stand. Progression models in resistance training for healthy adults. Med. Sci. Sports Exerc. 2009;41:687-708.
↑ 3.03.13.2da Silva D. Curty V. Areas J. Souza S. Hackney A. Machado M. Comparison of DeLorme with Oxford Resistance training techniques : Effects of training of muscle damage markers. Biol. Sport 2010; 27:77-81
↑Fish D. Krabak B. Johnson-Greene D. Delateur B. Optimal resistance training: comparison of DeLorme with Oxford techniques. Am. J. Phys. Med. Rehabil. 2003;82:903-909.
Carpal tunnel syndrome (CTS) is the most common peripheral nerve entrapment word wide. The general trend for this condition is progressive worsening, although spontaneous regression of symptoms is possible. Patients can be diagnosed quickly and respond well to treatment but the best means of integrating clinical, functional, and anatomical information for selecting treatment choices has not yet been identified.[1][2]
Clinically Relevant Anatomy
Fig.1 Median nerve compression.
Walls
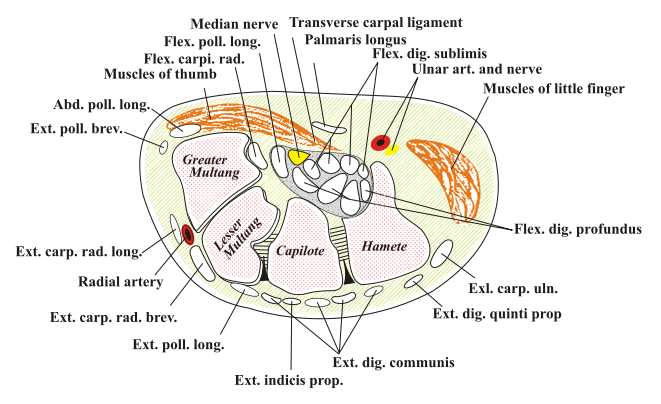
The carpal tunnel (CT) is formed by non extendable osteofibrous wall surrounding its content. The wall of the tunnel tunnel consists of carpal bones, joint capsule, carpal ligamets, flexor carpi radialis tendon and the flexor retinaculum. Carpal bones form an arch like base for the tunnel. Flexor retinaculum spanning from the pisiform bone and the hamulus of the hamate bone to the scaphoid and the trapezium complete and close the tunnel. [3][4] The eight carpal bones are oriented in two rows between the ulna and radius and the metacarpal bones. These form an articulated connection between the forearm and the hand.
Content
CT allows passage of multiple structures between hand and proximal segments of body (Picture 2). Tendons of flexor digitorum profundus, flexor digitorum superficialis and flexor pollicis longus muscles and the median nerve form the content of carpal tunnel. The median nerve passes from the forearm to the palmar aspect of the hand, Its sensory axons convey sensory stimulation for median nerve distribution consisting of palmar aspect of thumb and fingers, except for the fifth digit and ulnar half of fourth digit. Motor axons of median nerve supply the muscles of thenar eminence. [5]
The estimated prevalence of CTS is 4-5% of the population.There are two peak age frequencies: the first and biggest peak is between 45 and 59 years of which 75% is female. The second age peak is between 75 and 84 years, of which 64% is femal.Most cases of CTS are idiopathic, A portion of incidences of CTS are caused by pathological changes in structures passing through the carpal tunnel or the tissues forming it’s walls. Finally, considerable proportion of CTS cases are linked to pathological demands on wrist motion.
Idiopatic carpal tunnel syndrome
Idiopathic CTS occurs more frequently in females (65–80%) and between the ages of 40 and 60 years; 50–60% of the cases are bilateral.[6]
The bilateral characteristic increases in frequency with the duration of symptoms.[7]
Idiopathic CTS is correlated with hypertrophy of the synovial membrane of the flexor tendons caused by degeneration of the connective tissue, with vascular sclerosis, edema and collagen fragmentation.[8] The histological changes were thought to be suggestive of dynamic factors as repetitive strain.
Predisposing factors based on meta-analyses conducted in 2002[9] and 2008,[10] include:
sex
age
genetic and anthropometric factors (size of the carpal tunnel) were of most importance followed by other correctable predisposing factors of clinical importance as:
besity
smoking
excessive alcohol consumption
repetitive manual activities and exposure to vibrations and cold temperatures were the least important and of little clinical relevance
Secondary carpal tunnel syndrome
Abnormalities of the walls of CT
Any condition that modifies the walls of the carpal tunnel may cause compression of the median nerve.[11]
Abnormalities of the shape or position of the carpal bones: dislocation or subluxation of the carpus[11][12]
Abnormalities of the shape of the distal extremity of the radius: fractures (translation of more than 35%)[13] or skewed consolidation of the distal radius; osteosynthesis material on the anterior face of the radius;[14]
Joint abnormalities: wrist arthrosis,[15] inflammatory arthritis[16] (due to synovial hypertrophy, bone deformation an/or carpal shortening), infectious arthritis,[17] rhizarthrosis[18] or villonodular synovitis[19]
Inflammatory tenosynovitis: inflammatory rheumatism[16] lupus and infection
Metabolic tenosynovitis: diabetes mellitus[21] (abnormality of collagen turnover), primary or secondary amyloidosis (chronic hemodialysis with deposition of beta-2-microglobulin),[22] gout[23] and chondrocalcinosis;[24]
Abnormalities of fluid distribution: pregnancy[25][26] in 0.34% to 25% of the cases, especially in the third trimester, with frequent signs of deficit in 37–85% of the cases; hypothyroidism[27] and chronic kidney failure (arteriovenous fistula).[22]
Abnormal or supernumerary muscle: deep palmar muscle[28] intratunnel position of the muscle body of the superficial flexor[29] or proximal extension of the muscle body of the lumbrical muscles[30]
Persistent arterial hypertrophy of the median nerve
Intratunnel tumor: lipoma, synovial cyst, synovial sarcoma or neural tumor (schwannoma, neurofibroma or lipofibroma);
Hematoma: hemophilia[31] anticoagulant accident[32] or trauma[33]
The pressure inside the carpal tunnel increases during wrist extension and flexion[35] Repetitive extension and flexion movements of the wrist, along with flexion of the fingers and supination of the forearm, have been implicated in this increase[36] Incursions of muscle bodies from the superficial and deep flexors of the fingers, when the wrist and fingers are extended, have been found in 50% of the cases This particular movement can be seen in occupational pathological conditions[37]
Computer work and CTS
No increase in the prevalence of CTS in cases of working on computers for more than 15 h per week has been observed. A tendency toward increased prevalence has been demonstrated in cases of working on computers for more than 20 h per week[38]
Exposure to vibration
Exposure to vibration is one of the lesser predisposing factors.[27][10] The ultrastructural consequences comprise microcirculatory compression problems and intraneural edema following injury of the myelin and axons.
Occupational factors
Occupational biomechanical factors play a substantial role in the causation of CTS. Data from current primary studies on dose-response suggest that the risk of CTS increases with the [39]
Acute CTS
Etiologies:
Trauma: displacement due to fracturing of the distal radius or dislocation of the wrist;
Infection;
Hemorrhage due to overdose of anticoagulant or in cases of hemophilia;
High-pressure injection;
Acute thrombosis of the artery of the median nerve;
CTS onset is generally gradual with tingling or numbness in median nerve distribution of affected hand. Fig.3. [41][42][43] Patients may notice aggravation of symptoms with static gripping of objects as phone or steering wheel but also at night or early in the morning. [42][43] Many patients will report improvement of symptoms following shaking or flicking of their hand.
As the disorder progresses, the feeling of tingling or numbness may become constant and patients may complain of burning pain. [42] The final symptoms are weakness and atrophy of muscles thenar eminence. These combined effects of sensory deprivation and weakness may result in complaint of clumsiness and loss of grip and pinch strength or dropping things, [42]
Differential diagnosis
Fig. 4. Location of C7 dermatome. Note overlap with median nerve sensory distribution of hand.
Process of differential diagnosis should give consideration to all conditions which could potentially cause a dysfunction of median nerve, or its contributories in brachial plexus, C 5 to 8 nerve roots and central nervous system. For example: an injury of nn. digitales in the palm, radiculopathy will overlap with CTS in location of paraesthesia of hand as demonstrated in Fig. 3 and 4.
Other conditions to be aware of when diagnosing CTS include:
Diagnostic procedures
Electroneuromyography (ENMG) examination[41] is used to examine the sensory and motor nerve conductance of the median nerve. It also highlights the elective weakening in passing through the carpal tunnel. It is considered abnormal when there is a diminished sensory conduction velocity between the wrist, the palm of the hand and the fingers. This test may be used to diagnose the condition and rule out other pathologies. [2]
Electromyogram (EMG) of the muscles innervated by the median nerve measures electrical dischargers produced in the muscles. This test can determine if there is any muscle damage and can rule out other conditions. [46][47]
Ultrasonography can identify space-occupying lesion in and around the median nerve. The test can confirm abnormalities that can diagnose CTS and help guide steroid injections into the carpal tunnel. [41][48]
X-ray is recommended to exclude other causes of wrist pain like arthritis or bony pathology. [2]
Outcome measures
There are several questionnaires available to determine the outcome measures for CTS. The four questionnaires below are all supported by studies with level of evidence 2A or 2B. Only the study of Levine et al. [49], describing the BCTQ, has level of evidence 4. This questionnaire is, however supported by other, higher level studies as well.
1. Boston Carpal Tunnel Questionnaire (The BCTQ or the Levine Scale, originally developed by Levine et al. (1993) [49], is the most commonly used outcome measure in the assessment of CTS patients. It can be self-, interview- or telephone-administered. The questionnaire comprises of two scales: the Symptom Severity Scale (SSS) and the Functional Status Scale (FSS). [50][51]
The SSS consist of 11 questions, scored on a five-point rating scale, for the evaluation of pain, test-retest reliability of paraesthesia, numbness, weakness, nocturnal symptoms and overall function status. [50][51]
The FSS rates 8 functional activities on difficulty level, also scored on a five-point rating scale. The overall score for both scales is calculated as the mean of the items. [51] The reliability, validity and responsiveness of the BCTQ has been found to be very good by several studies, such as the report of the University of Oxford16 and the studies of Sambandam et al. [51], Bakhsh et al. [52] and Greenslade et al. [53].
2. Disability of Hand and Shoulder (DASH) Questionnaire The DASH-questionnaire is a self-, interview- or telephone-administered region-specific outcome instrument developed as a measure of self-rated upper-extremity disability and symptoms. The DASH is a 30-item scale, each scored on a 5-point Likert scale and overall scored on a scale from 0 (no disability) to 100 (maximum disability). It consists of two dimensions: Physical Functioning and Symptoms. The DASH is not specific for CTS, but can detect and differentiate small and large changes in disability over time after surgery in patients with several upper extremity musculoskeletal disorders. [50] The DASH questionnaire is also found to be a valid and reliable test with good responsiveness. [50][51][53][54] Bakhsh et al. [52] however found the DASH questionnaire to be less responsive than the BCTQ.
3. Michigan Hand Outcomes Questionnaire (MHQ) The MHQ is a self-, interview- or telephone-administered questionnaire used to assess the outcome for various hand disorders. [50] It consists of 37 items, grouped into 6 domains: overall hand function, activity of daily living, pain, work performance, aesthetics and patient satisfaction with hand function. All questions are scored from 1 to 5, with high scores denoting better performance, except for the pain scale, in which a higher score means more pain. The score of each scale is converted to a score from 0 to 100. [50][51] The MHQ is found to be a valid and reliable measurement with good responsiveness. [50][51]
A short 12 item version was also validated for CTS and several other common hand conditions to reduce the burden and promote its use in clinical setting.[55]
4. Patient Evaluation Measures (PEM) The PEM is a self-, interview- or telephone-administered questionnaire to measure physical health. It consists of 3 components (patient’s opinion on delivery of care, hand health profile, overall assessment) and a total of 18 items scored on a 7-point scale. Low scores indicate positive outcomes.16 17 Hobby et al.20 found this instrument to be valid and reliable and to have good responsiveness. [50][51]
Examination
Clinical prediction rules (CPR), specifically for the Carpal Tunnel Syndrome, are a reliable examination method. It consists of five tests. Wainner et al. [56] found that the CPR is more useful for diagnosis of CTS than any single test item. Using CPR results is posttest probability changes up to 56%.
Other than the CPR, there are several provocative tests and the thenar atrophy observation that can be used in the clinical examination of a CTS patient. In Table 2 [58] you find the sensitivity and specificity rates of all the tests explained below.
Table 2: Diagnostic Parameters of Clinical Tests for Carpal Tunnel Syndrome
1. [60], the patient holds his forearm vertically and lets his wrist drop down in 90° flexion [61]. The arm can also be held horizontally in front of the patient with the wrist hanging down. [62] Another common way of executing the test is to hold both wrists against each other in 90° flexion with elbows also flexed and fingers pointing in the patient’s direction. [63][64] The Reverse Phalen’s test, where the patient holds his wrist and fingers in full extension, provokes the same symptoms as the original test, which are the symptoms that are usually experienced by patients with CTS, such as tingling, paresthesia or pain in the fingers. [61][62]
3. Hand elevation test ([61] The test is positive when the patient experiences typical CTS symptoms, such as a numb or tingling feeling in the fingers or pain or stiffness in the fingers, palm or wrist. Some patients also experience soreness in the shoulder. [65]
This test is only considered meaningful if the results can be duplicated by other, more specific CTS tests. [65]
4. Scratch Collapse Test (CTS-6 Lax/Sringent) Cheng et al. [66] introduced this test in 2008 as an improved method to diagnose CTS among other syndromes. The test is executed with the patient facing the examiner with his arms adducted, elbows flexed and hands outstretched with the wrists in neutral position. The patient has to resist the external rotation movement the examiner is trying to make by pushing both the patient’s forearms out. The examiner then scratches the median nerve at carpal tunnel level and the previous exercise is repeated. A brief loss of resistance against the external rotation force of the affected side after scratching the median nerve is considered a positive scratch collapse test. [66]
Video of the Scratch Collapse Test:
5. Durkan’s Carpal Compression Test The examiner externally applies pressure directly over the carpal tunnel. This test is also positive when the typical CTS symptoms occur while the pressure is applied. [61]
Medical Management
Non-surgical treatment comprises oral steroids [67][68], corticosteroid injections [68], NSAID [67][68], diuretics [67][69], vitamin B6 [67] and splinting/hand brace [67][68][69]. Reviews show that there is moderate and strong evidence for the effectiveness for curing CTS using oral and local steroids. [67][68][69] Huisstede et al [68] says that for both treatments no evidence was found for long term effectiveness. Diuretics, NSAID and vitamin B6 turn out to be ineffective [67][68][69]. There is limited [67] to moderate[69] evidence of the effectiveness of splinting in short term. Huisstede et al [68] claim that number of nonsurgical interventions benefit CTS in the short term, but there is sparse evidence on the midterm and long-term effectiveness of these interventions[42][68]
Huistede et al [70] concluded that surgical treatment seems to be more effective than splinting and anti-inflammatory drugs plus hand therapy in the midterm and long term to treat CTS [42][68]. However, there is no unequivocal evidence that suggestsone surgical treatment is more effective than the other[42].
The two main manners to decompress the median nerve by surgery are the [71] says that with both techniques (OCTR and ECTR) the structural complications for nerves, blood vessels or tendons are low. According to Chen et al [72] there are no obvious statistical differences in relief of symptoms (pain en paraesthesia), recovery of grip strength a reoperation rate. Though, two articles with moderate to strong level of evidence declares the ECTR causes a faster return to work [72][73] and a better recovery of pinch strength.
Physical Therapy management
Patients with mild to moderate symptoms do not need to be immediately operated but can be effectively treated in a primary care environment [74][75] Physical therapy typically consists of modifications of activities and the work place (ergonomic modifications) [74][75], patient education, carpal bone and [76],, ultrasound [67][68][76] and electromagnetic field therapy [67][68] and splinting.[77]
It’s important to mention that, in general, the evidence of the effectiveness of the exercise and mobilization interventions is limited and very low in quality. The physical therapist should always inform the patient about the limited evidence of effectiveness and safety as well as availability of surgical option without the pre-requite conservative therapy where appropriate. [76].
The effectiveness of ultrasound varies between the studies and most of the time the evidence is low. According to Page et al [78] there’s poor and limited evidence about the effect of therapeutic ultrasound. There is insufficient evidence that therapeutic ultrasound has a greater benefit than other non-surgical treatments, such as splinting, exercises or oral drugs.
It is important to pay attention to the cause of the CTS. Physical therapists should give advice in task modification, like taking fufficient rest and variation of movements. Burke et al [75] declare that often simple obvious alterations to the working practice can be beneficial in controlling milder symptoms of CTS.
Peter et al [79] declare that evidence about post-operative rehabilitation is also limited. Their reviewed interventions handle physical applications, differences between kinds of immobilisation and multimodal hand therapy. None of them seems to have a prevailing benefit.
Clinical Bottom Line
Patients may benefit form physiotherapy based treatment with goals of CTS symptom reduction and functional gains, provided that:
their symptoms are intermittent and not rapidly worsening or if their CTS etiology is highly suggestive of possibility of remission as in example of pregnancy related CTS
patients are informed about the lack of high quality evidence for effectiveness and safety of therapeutic modalities used by physiotherapists,
Treatment should be discontinued when shown to be ineffective and appropriate, evidence based discharge recommendations should be made.
CTS symptoms typically escalate over a longer term despite conservative treatment. Surgical interventions for appropriate patients have been shown to be safe and more effective than any conservative intervention, Clinicians should be aware that constant tingling or numbness is associated with significant compression of median nerve. Prolonged duration of such symptoms may lead to irreversible changes in its internal structure, affecting effectiveness of surgery and leaving individuals with chronic symptoms and muscle atrophy of thenar eminence. Patients should be followed by their general practitioners to discuss surgical treatment options when necessary and desired.
References
↑Padua L, Coraci D, Erra C, Pazzaglia C, Paolasso I, Loreti C, Caliandro P, Hobson-Webb LD. Carpal tunnel syndrome: clinical features, diagnosis, and management. The Lancet Neurology. 2016 Nov 1;15(12):1273-84.
↑ 2.02.12.22.3Chammas M, Boretto J, Burmann LM, Ramos RM, Neto FCS, Silva JB. Carpal tunnel syndrome – part 1 (anatomy, physiology, etiology and diagnosis). Revista brasileira de Ortopedia (English edition) 2014 September-October; 49 (5):429-436.
↑Shiel WC. Carpal tunnel syndrome [internet]. 2008 [2013 November 13 ; 2015 April 4]. Available from : ↑Moses KP, Banks JC, Nava PB, Petersen D. Altals of clinical gross anatomy. Elsevier Mosby; 2008. Chapter 23, Wrist and hand joints; p.260-265.
↑Carpal tunnel syndrome fact sheet [internet]. Bethesda; 2012 July [2015 April 17; 2015 april 20]. Available from: ↑Michelsen H, Posner MA. Medical history of carpal tunnel syndrome. Hand clinics. 2002 May 1;18(2):257-68.
↑Bagatur A.E., Zorer G. The carpal tunnel syndrome is a bilateral disorder. J Bone Joint Surg Br. 2001;83(5):655–658.
↑Schuind F., Ventura M., Pasteels J.L. Idiopathic carpal tunnel syndrome: histologic study of flexor tendon synovium. J Hand Surg Am. 1990;15(3):497–503.
↑Falkiner S., Myers S. When exactly can carpal tunnel syndrome be considered work-related? ANZ J Surg. 2002;72(3):204–209.
↑ 10.010.1Lozano-Calderon S., Anthony S., Ring D. The quality and strength of evidence for etiology: example of carpal tunnel syndrome. J Hand Surg Am. 2008;33(4):525–538.
↑ 11.011.1Knoll V.D., Allan C., Trumble T.E. Trans-scaphoid perilunate fracture dislocations: results of screw fixation of the scaphoid and lunotriquetral repair with a dorsal approach. J Hand Surg Am. 2005;30(6):1145–1152.
↑Monsivais J.J., Scully S. Rotary subluxation of the scaphoid resulting in persistent carpal tunnel syndrome. J Hand Surg Am. 1992;17(4):642–644.
↑Dyer G., Lozano-Calderon S., Gannon C., Baratz M., Ring D. Predictors of acute carpal tunnel syndrome associated with fracture of the distal radius. J Hand Surg Am. 2008;33(8):1309–1313.
↑Henry M., Stutz C. A prospective plan to minimise median nerve related complications associated with operatively treated distal radius fractures. Hand Surg. 2007;12(3):199–204.
↑Fassler P.R., Stern P.J., Kiefhaber T.R. Asymptomatic SLAC wrist: does it exist? J Hand Surg Am. 1993;18(4):682–686.
↑ 16.016.1Chammas M. Le poignet rhumatoide. Chir Main. 2005;24(6):275–298.
↑Hassanpour S.E., Gousheh J. Mycobacterium tuberculosis-induced carpal tunnel syndrome: management and follow-up evaluation. J Hand Surg Am. 2006;31(4):575–579.
↑Brutus J.P., Baeten Y., Chahidi N., Kinnen L., Ledoux P., Moermans J.P. Atypical mycobacterial infections of the hand: report of eight cases and literature review. Chir Main. 2001;20(4):280–286.
↑Chidgey L.K., Szabo R.M., Wiese D.A. Acute carpal tunnel syndrome caused by pigmented villonodular synovitis of the wrist. Clin Orthop Relat Res. 1988;(228):254–257.
↑Jenkins P.J., Sohaib S.A., Akker S., Phillips R.R., Spillane K., Wass J.A. The pathology of median neuropathy in acromegaly. Ann Intern Med. 2000;133(3):197–201.
↑Chammas M., Bousquet P., Renard E., Poirier J.L., Jaffiol C., Allieu Y. Dupuytren’s disease, carpal tunnel syndrome, trigger finger, and diabetes mellitus. J Hand Surg Am. 1995;20(1):109–114.
↑ 22.022.1Allieu Y., Chammas M., Idoux O., Hixson M., Mion C. Carpal tunnel syndrome and amyloid tenosynovitis in patients undergoing chronic hemodialysis. Evaluation and treatment apropos of 130 cases. Ann Chir Main Memb Super. 1994;13(2):113–121.
↑Schuind F.A., Clermont D., Stallenberg B., Remmelink M., Pasteels J.L. Gouty involvement of flexor tendons. Chir Main. 2003;22(1):46–50
↑Gerster J.C., Lagier R., Boivin G., Schneider C. Carpal tunnel syndrome in chondrocalcinosis of the wrist. Clinical and histologic study. Arthritis Rheum. 1980;23(8):926–931.
↑Stolp-Smith K.A., Pascoe M.K., Ogburn P.L., Jr. Carpal tunnel syndrome in pregnancy: frequency, severity, and prognosis. Arch Phys Med Rehabil. 1998;79(10):1285–1287.
↑M’Bappé P. Complications neurologiques de la grossesse (sciatique exclue) Rev Rhum Ed Fr. 2005;72:719–724.
↑Schon R., Kraus E., Boller O., Kampe A. Anomalous muscle belly of the flexor digitorum superficialis associated with carpal tunnel syndrome: case report. Neurosurgery. 1992;31(5):969–970.
↑Pierre-Jerome C., Bekkelund S.I., Husby G., Mellgren S.I., Osteaux M., Nordstrom R. MRI of anatomical variants of the wrist in women. Surg Radiol Anat. 1996;18(1):37–41.
↑Moneim M.S., Gribble T.J. Carpal tunnel syndrome in hemophilia. J Hand Surg Am. 1984;9(4):580–583.
↑Bindiger A., Zelnik J., Kuschner S., Gellman H. Spontaneous acute carpal tunnel syndrome in an anticoagulated patient. Bull Hosp Jt Dis. 1995;54(1):52–53.
↑Paley D., McMurtry R.Y. Median nerve compression by volarly displaced fragments of the distal radius. Clin Orthop Relat Res. 1987;(215):139–147.
↑Bland J.D. The relationship of obesity, age, and carpal tunnel syndrome: more complex than was thought? Muscle Nerve. 2005;32(4):527–532.
↑Gelberman R.H., Hergenroeder P.T., Hargens A.R., Lundborg G.N., Akeson W.H. The carpal tunnel syndrome. A study of carpal canal pressures. J Bone Joint Surg Am. 1981;63(3):380–383.
↑Mackinnon S.E. Pathophysiology of nerve compression. Hand Clin. 2002;18(2):231–241.
↑Kerwin G., Williams C.S., Seiler J.G., 3rd. The pathophysiology of carpal tunnel syndrome. Hand Clin. 1996;12(2):243–251.
↑Andersen J.H., Fallentin N., Thomsen J.F., Mikkelsen S. Risk factors for neck and upper extremity disorders among computers users and the effect of interventions: an overview of systematic reviews. PLoS ONE. 2011;6(5):e19691.
↑Kozak A, Schedlbauer G, Wirth T, Euler U, Westermann C, Nienhaus A. Association between work-related biomechanical risk factors and the occurrence of carpal tunnel syndrome: an overview of systematic reviews and a meta-analysis of current research. BMC musculoskeletal disorders. 2015 Dec;16(1):231.
↑Gray, Henry. Anatomy of the Human Body. Philadelphia: Lea & Febiger, 1918; Bartleby.com, 2000. www.bartleby.com/107/. [Date of Printout].
↑ 41.041.141.2Jesus Filho AG, do Nascimento BF. Comparative study between physical examination, electroneuromyography and ultrasonography in diagnosing carpal tunnel syndrome. Revista Brasileira de Ortopedia (English Edition). 2014 September–October; 49(5): 446–451.
↑ 42.042.142.242.342.442.542.6Ashworth NL, MBChB. Carpal Tunnel Syndrome Clinical Presentation [Internet]. 1994 [Updated 2014 Aug 25; cited 2015 March 20].fckLRAvailable from:fckLRhttp://emedicine.medscape.com/article/327330-clinical.
↑ 43.043.1Krom de M.C.T.F.M., MD, KnipschildP.G. Prof. Efficacy of provocative tests for diagnosis of carpal tunnel syndrome. The Lancet. 1990 Feb 17; Vol.335 Issue 8686: 393-395.
↑ 44.044.144.2Amadio P. Differential Diagnosis of Carpal Tunnel Syndrome. Carpal Tunnel Syndrome. 2007. Chapter 41, Differential diagnosis of carpal Tunnel; p.89-94
↑Ashworth NL, MBChB. Carpal Tunnel Syndrome Differential Diagnoses [Internet]. 1994 [Updated 2014 Aug 25; cited 2015March 20] Available from: ↑Visser LH, Smidt MH, Lee ML. High-resolution sonography versus EMG in the diagnosis of carpal tunnel syndrome. J Neurol Neurosurg Psychiatry. 2008;79:63-67.
↑Simpson JA. Electrical signs in the diagnosis of carpal tunnel and related syndromes. J Neurol Neurosurg Psychiatry. 1956 Nov; 19(4):275-280.
↑Ashworth NL, MBChB. Carpal Tunnel Syndrome Workup [Internet]. 1994 [Updated 2014 Aug 25; cited 2015 March 20].fckLRAvailable from: ↑ 49.049.1Levine DW, Simmons BP, Koris MJ, Daltroy LH, Hohl GG, Fossel AH, Katz JN. A self-administered questionnaire for the assessment of severity of symptoms and functional status in carpal tunnel syndrome. J Bone Surg Am. 1993 Nov; 75(11):1585-92.
↑ 50.050.150.250.350.450.550.650.7Hadi M, Gibbons E, Fitzpatrick R. A structured review of patient-reported outcome measures for procedures for carpal tunnel syndrome. Oxford: Departmet of Public Health (University of Oxford); 2011. 33p.
↑ 51.051.151.251.351.451.551.651.7Sambandam SN, Priyanka P, Gul A, Ilango B. Critical analysis of outcome measures used in the assessment of carpal tunnel sundrome. Int Orthop. 2008 Aug; 32(4):497-504.
↑ 52.052.1Bakhsh H, Ibrahim I, Khan W, Smitham P, Goddard N. Assessment of validity, reliability, responsiveness and bias of three commonly used patient-reported outcome measures in carpal tunnel syndrome. Ortop traumatol Rehabil. 2012 Jul/Aug; 14(4):335-340.
↑ 53.053.1Greenslade JR, Mehta RL, Belward P, Warwick DJ. Dash and Boston questionnaire assessment of carpal tunnel syndrome outcome: what is the responsiveness of an outcome questionnaire? JHS. 2004 Apr; 29(2):159-164.
↑Hobby JL, Watts C, Elliot D. Validity and responsiveness of the patient evaluation measure as an outcome measure for carpal tunnel syndrome. J Hand Surg Br. 2005 Aug; 30(4):350-354.
↑Shauver MJ, Chung KC. The Michigan Hand Outcomes Questionnaire (MHQ) after 15 years of field trial. Plastic and reconstructive surgery. 2013 May;131(5):779e.
↑Wainner RS, Fritz JM, Irrgang JJ, Delitto A, Allison S, Boninger ML. Development of a clinical prediction rule for the diagnosis of carpal tunnel syndrome. Archives of Physical Medicine and Rehabilitation. 2005 Apr; 86(4): 609-618.
↑Physiotutors. Wainner Clinical Prediction Rule (CPR) | Carpal Tunnel Syndrome (CTS). Available from: ↑ 58.058.1Makanji HS, Becker SJE, Mudgal CS, Jupiter JB, Ring D. Evaluation of the scratch collapse test for the diagnosis of carpal tunnel syndrome. JHS. 2014 Feb; 39(2):181-186.
↑Phalen GS. The Carpal-tunnel Syndrome: Clinical Evaluation of 598 Hands. Clinical Orthopaedics. 1972 Mar/Apr; 83:29-40.
↑ 60.060.1Phalen GS. The Carpal-Tunnel Syndrome – seventeen years’ of experience in diagnosis and treatment of six hundredfifty-four hands. J Bone Joint Surg Am. 1966 Mar; 48(2):211-228.
↑ 61.061.161.261.361.4Diagnosing CTS; Provocative tests [internet]. NHS; 2010 [Updated 2011 June 11]. Available from: ↑ 62.062.162.2Romito K. Physical Exam for Carpal Tunnel Syndrome [internet]. Healthwise; 2005 [Updated 2012 Oct 2]. Available from: fckLRhttp://www.webmd.com/pain-management/carpal-tunnel/physical-exam-for-carpal-tunnel-syndrome.
↑ 63.063.1Urbano FL. Tinel’s sign and Phalen’s Maneuver: Physical Signs of Carpal Tunnel Syndrome. Hospital Physician. 2000 Jul: 39-44.
↑Wolgin MA. Carpal Tunnel Syndrome ↑ 65.065.1How to Use a Hand Elevation Test to Detect Carpal Tunnel Syndrome [internet]. Demand Media; 1999-2015. Available from: ↑ 66.066.1Cheng CJ, Mackinnon-Patterson B, Beck JL, Mackinnon SE. Scratch Collapse Test for Evaluation of Carpal and Cubital Tunnel Syndrome. JHS. 2008 Nov; 33(9):1518-1524.
↑ 67.067.167.267.367.467.567.667.767.867.9O’Connor D, Marshall SC, Massy-Westropp N, Pitt V. Non-surgical treatment (other than steroid injection) for carpal tunnel syndrome (Review). The Cochrane database of systematic reviews. 2012; volume (7):1-106.
↑ 68.0068.0168.0268.0368.0468.0568.0668.0768.0868.0968.1068.11Huisstede BM, Hoogvliet P, Randsdorp MS, Glerum S, van Middelknoop M, Koes BW. Carpal Tunnel Syndrome. Part I: Effectiveness of Nonsurgical Treatments–A Systematic Review. Archives of physical medicine and rehabilitation. 2010 Jul; 91(7):981-1004.
↑ 69.069.169.269.369.4Piazzini DB, Aprile I, Ferrara PE, Bertolini C, Tonali P, Maggi L, Rabini A, Piantelli S, Padua L. A systematic review of conservative treatment of carpal tunnel syndrome. Clinical rehabilitation. 2007 Apr; 21(4):299-314.
↑Huisstede BM, Randsdorp MS, Coert JH, Glerum S, van Middelknoop M, Koes BW. Carpal Tunnel Syndrome. Part II: Effectiveness of Surgical Treatments—A Systematic Review. Archives of physical medicine and rehabilitation. 2010 Jul; 91(7):1005-24.
↑Benson LS, Bare AA, Nagle DJ, Harder VS, Williams CS, Visotskv JL. Complications of Endoscopic and Open Carpal Tunnel Release. Arthroscopy. 2006 Sep; 22(9):919-24.
↑ 72.072.1Chen L, Duan X, Huang X, Lv J, Peng K, Xiang Z. Effectiveness and safety of endoscopic versus open carpal tunnel decompression. Archives of orthopaedic and trauma surgery. 2014 Apr; 134(4):585-93.
↑Saw NL, Jones S, Shepstone L, Meyer M, Chapman PG, Logan AM. Early outcome and cost-effectiveness of endoscopic versus open carpal tunnel release: a randomized prospective trial. Journal of hand surgery. 2003 Oct; 28(5):444-9.
↑ 74.074.1Oskouei AE, Talebi GA, Shakouri SK, Ghabili K. Effects of Neuromobilization Maneuver on Clinical and Electrophysiological Measures of Patients with Carpal Tunnel Syndrome. Journal of physical therapy science. 2014 Jul; 26(7):1017-22.
↑ 75.075.175.2Burke FD, Ellis J, McKenna H, Bradley MJ. Primary care management of carpal tunnel syndrome. Postgraduate medical journal. 2003 Aug; 79 (934):433-7.
↑ 76.076.176.2Page MJ, O’Connor D, Pitt V, Massy-Westropp N. Exercise and mobilisation interventions for carpal tunnel syndrome. Cochrane Database Syst Rev. 2012;6:CD009899.
↑Page MJ, Massy-Westropp N, O’Connor D, Pitt V. Splinting for carpal tunnel syndrome.
↑Page MJ, O’Connor D, Pitt V, Massey-Westropp N. Therapeutic ultrasound for carpal tunnel syndrome (Review). The Cochrane database of systematic reviews. 2013 Mar; 28(3):1-156.
↑Peters S, Page MJ, Coppieters MW, Ross M, Johnston V. Rehabilitation following carpal tunnel release (Review). The Cochrane database of systematic reviews. 2013 Jun; 5(6): 1-147.
Para testar a integridade do ligamento cruzado anterior (LCA) [1]
Técnica
O paciente está deitado em um pedestal com os quadris flexionados a 45 graus, os joelhos flexionados a 90 graus e os pés apoiados no pedestal. O examinador está sentado nos dedos da extremidade testada para ajudar a estabilizá-lo. O examinador segura a perna proximal, logo abaixo do platô tibial ou linha articular tibiofemoral, e tenta traduzir a parte anterior da perna. O teste é considerado positivo se houver falta de sensibilidade final ou excesso de translação anterior em relação ao lado contralateral. [2]
Evidência
Uma fonte reporta sensibilidade e especificidade como .41-.91 e .86-1.0 respectivamente, com um -LR de .09-.62 e um + LR de 5.4-8.2. [2] No entanto, uma meta-análise recente relata a sensibilidade e especificidade como .18-.92 e .78-.98, respectivamente. [5] Scholten et al concluíram que, com base na estatística do valor preditivo, não se pôde tirar conclusões sólidas sobre se o teste da gaveta anterior era bom para determinar ou descartar a presença de uma ruptura do LCA. [5] Outra pesquisa recente identificou o teste de gaveta anterior como um teste mais eficaz para identificar condições crônicas, com uma sensibilidade e especificidade de 0,92 e 0,91. [6]
A frouxidão do LCA ou a instabilidade do joelho depende das forças aplicadas ao joelho e aumenta com força maior. Estes são diferentes na investigação clínica e durante a atividade moderada ou extenuante. Portanto, o teste da gaveta anterior nem sempre pode prever a perda do LCA ou a instabilidade articular que existe durante a atividade extenuante. A frouxidão articular pode ser reduzida quando, após a lesão, a pessoa reduz seu nível de atividade. Assim, a estabilidade funcional pode ser mantida. [7]
Katz e Fingeroth [1] relataram que o teste de tração anterior do joelho tem uma acurácia diagnóstica de rupturas agudas do LCA (dentro de 2 semanas de exame) de: 22,2% de sensibilidade e> 95% de especificidade.O estudo relatou a acurácia diagnóstica de LCR subaguda / crônica rupturas (mais de 2 semanas antes do exame) é: sensibilidade de 40,9% e especificidade de 98,4%. É importante notar que neste estudo todos os exames foram realizados sob anestesia; Assim, a acurácia diagnóstica na prática clínica fisioterapêutica pode ser menor. O teste de tração anterior do joelho, apesar de amplamente utilizado, é um mau indicador diagnóstico das rupturas do LCA, principalmente no quadro agudo.
Os testes com maior probabilidade de fornecer um resultado preciso são o pivot shift ou o Lachman . [1][8]
Referências
Katz JW, Fingeroth RJ.↑ 1,01,11,2Katz JW, Fingeroth RJ.A acurácia diagnóstica das rupturas do ligamento cruzado anterior comparando o teste de Lachman, o sinal da gaveta anterior e o teste do pivot shift nas lesões agudas e crônicas do joelho.The American Journal of Sports Medicine 1986; 14: 88-91.fckLRhttp: //ajs.sagepub.com/content/14/1/88.short (acessado em 18 de julho de 2013).
Flynn TW, Cleland JA, Whitman JM.↑ 2,02,1Flynn TW, Cleland JA, Whitman JM.Guia do usuário para o exame musculoesquelético: fundamentos para o clínico baseado em evidências.Estados Unidos: Evidence in Motion;2008.
Physiotutors.↑Fisioterapeutas.Teste da gaveta anterior⎟Ruptura do ligamento cruzado anterior.Disponível em:
Katie Yost.↑Katie Yost.
Exame Físico do Joelho.Disponível em:
Scholten PJPM, Opstelten W, van der Plas CG, Bijl D, Deville WLJM and Bouter LM.↑ 5.05.1Scholten PJPM, Opstelten W, van der Plas CG, Bijl D, Deville WLJM e Bouter LM.Exatidão dos testes de diagnóstico físico para avaliação das rupturas do ligamento cruzado anterior: uma meta-análise.J Fam Pract.2003; 52: 689-694.
Benjaminse A, Gokeler A van der Schans CP.↑Benjaminse A, Gokeler A van der Schans CP.Diagnóstico clínico de uma ruptura do ligamento cruzado anterior: uma meta-análise.J Orthop Sports Phys Ther.2006; 36 (5): 267-88.
BUTLER DL, NOYES DR, GROOD ES, Ligamentous restraints to anterior-posterior drawer in the human knee.↑MORDOMO DL, NOYES DR, GROOD ES, Restrições ligamentosas à gaveta ântero-posterior no joelho humano.um estudo biomecânico, J Bone Joint Srug Am.1980; 62: 259-270
OSTROWSKI JA, Accuracy of 3 diagnostic tests for anterior cruciate ligament tears, Journal of Athletic Training, 2006, 41(1): 120-122↑OSTROWSKI JA, Exatidão de 3 testes diagnósticos para lesões do ligamento cruzado anterior, Journal of Athletic Training, 2006, 41 (1): 120-122
Uso da terapia por ondas de choque para o tratamento do linfedema associado ao câncer de mama: uma revisão sistemática
O linfedema associado ao câncer de mama é causa de prejuízo significativo da qualidade de vida deste grupo de pacientes e constitui complicação frequente das intervenções necessárias nesse tipo de câncer. Sabe-se que o tratamento utilizado no linfedema associado ao câncer de mama envolve a Terapia Física Complexa (TFC), cuja eficácia é limitada e não atua diretamente na patogênese dessa comorbidade. Conforme já demonstrado em alguns estudos, o uso da Terapia por Ondas de Choque (TOC) demonstra-se potencialmente benéfico para reduzir o linfedema pela indução de neoangiogênese e linfangiogênese.
Objetivo: Avaliar o impacto da TOC no tratamento do linfedema associado ao câncer de mama comparado ao uso da TFC.
Métodos: Foram utilizadas as seguintes bases de dados: PubMed/MedLine; BIREME; LILACS; The Cochrane Library e EMBASE, e através de busca manual de artigos. Adotou-se o método de pesquisa PICO e os descritoresMeshs ajustados conforme a respectiva base de dados.
Esta gostando do artigo “Uso da terapia por ondas de choque”, então confira também outros artigos completos abaixo:
Resultados: Foram encontrados um total de 262 artigos e selecionados por leitura do título ou resumo um total de 17 estudos. Seis foram excluídos por serem duplicatas, totalizando 11 artigos eleitos para verificação dos critérios de inclusão. Destes, nenhum artigo atendeu ao delineamento da metodologia proposta para esta revisão. Três deles se destacaram por se aproximarem mais da temática proposta e foram discutidos.
Conclusão: É necessária a realização de estudos com qualidade metodológica adequada para avaliar o potencial benefício do uso da TOC, visando contribuir para a composição de um tratamento mais eficaz, seguro e que atue na patogênese da doença.
Palavras-chave: Linfedema Relacionado a Câncer de Mama, Tratamento por Ondas de Choque Extracorpóreas, Drenagem Linfática Manual, Reabilitação
O curso de ondas de choque acontece sempre em um dia sendo de sábado das 8h30 às 18h30 com parte teórica e prática e os alunos saem aptos a aplicar a técnica !! Ministrante com grande conhecimento na área e incluso apostila colorida e certificado de conclusão !!
Artigo sobre a Quiropraxia – Confira esse Artigo Completo sobre a Quiropraxia:
Quiropraxia: É eficiente no tratamento de doenças? Revisão de Revisões Sistemáticas
A quiropraxia é uma medicina complementar que vem crescendo cada vez mais em diferentes países nas últimas décadas. Aborda a prevenção, diagnóstico e tratamento dos distúrbios do sistema neuromusculoesquelético e seus efeitos sobre a saúde do corpo inteiro.
Este estudo tem como objetivo avaliar a eficácia da quiropraxia no tratamento de diferentes doenças.
Para coletar dados, bancos de dados eletrônicos científicos, como Cochrane, Medline, Google Scholar e Scirus foram pesquisados e todas as revisões sistemáticas no campo da quiropraxia foram obtidas.
As revisões foram incluídas se estivessem especificamente relacionadas à eficácia do tratamento quiroprático, incluíam evidências de pelo menos um ensaio clínico, incluíam estudos randomizados e focalizavam uma doença específica.
Esta gostando desse Artigo sobre a Quiropraxia ? Confira também nosso curso de Quiropraxia Clínica – Clique no link no final da página !!!
Os dados da pesquisa, incluindo o nome do primeiro autor do artigo, tipo de doença, tipo de intervenção, número e tipos de pesquisas utilizadas, meta-análise, número de participantes e resultados gerais do estudo, foram extraídos, estudados e analisados.
Assim, a realização de estudos abrangentes com base em projetos de estudo mais confiáveis é altamente recomendada.
Artigo sobre a Quiropraxia – Quiropraxia é um tipo de medicina complementar com várias definições em diferentes artigos e outros recursos científicos. De acordo com Definição da Organização Mundial da Saúde (OMS), Quiropraxia é “uma profissão de saúde em causa com o diagnóstico, tratamento e prevenção de distúrbios do sistema neuromusculoesquelético, e os efeitos desses distúrbios em geral saúde”. Procedimentos de tratamento de Quiropraxia enfatize as técnicas manuais, incluindo ajuste e / ou manipulação articular, com um foco específico na subluxação.
A base da abordagem quiroprática para restauração e proteção da saúde é o relação entre estrutura, especificamente a coluna vertebral e sistema músculo-esquelético, e função, particularmente conforme coordenado pelo sistema nervoso. Em outras palavras, com base no abordagem quiropraxia, o corpo é considerado como um sistema neuromusculoesquelético em que desordem em uma parte do sistema perturba outras partes.
Portanto, distúrbios no corpo estrutura são removidos de modo que as tensões sobre o sistema nervoso do corpo pode ser aliviado e a saúde geral do corpo pode ser restaurada
Quiropraxia foi fundada por Daniel David Palmer nos Estados Unidos da América (EUA), em 1895, e gradualmente atraiu seus proponentes entre médicos e outros profissionais. Hoje em dia, Quiropraxia é ensinado em pelo menos 40 universidades faculdades, em 16 países diferentes (Tabela 1). Além disso, a maioria deles está localizada no EUA como é o local de nascimento da quiropraxia .
Com o tempo nos acostumamos com as dores e passamos a aceitar o fato de que, por conta do esporte, da idade ou da vida; já não somos mais os mesmos e decidimos parar com as atividades que nos causam dor, deixando de lado um esporte, uma prática ou um hobby que gostamos.
Entretanto, existem diversos tratamentos destinados à melhora dessas dores e lesões, que são capazes de melhorar os incômodos e de nos devolver a capacidade de fazer aquilo que amamos. E, dentre os mais eficazes deles está a Reabilitação Funcional, o tema deste artigo.
Acompanhe para saber tudo sobre esse tratamento. O que ele é, como funciona, pra quem é indicado e muito mais.
O que é Reabilitação Funcional?
A reabilitação funcional é um conjunto de técnicas utilizadas para devolver aos pacientes suas funções. Entendendo como funções as suas capacidades de andar, pular, correr, subir uma escada e se vestir, por exemplo.
São atividades diárias que são prejudicados por fatores como lesões, patologias, fraqueza muscular, disfunções articulares, padrões posturais da coluna e problemas respiratórios e do coração.
Portanto, a Reabilitação Funcional é uma forma de devolver ao paciente toda a liberdade para realizar suas atividades e voltar a ter uma vida normal, visando uma diminuição dos sintomas e, por consequência, a melhora dos movimentos.
Para isso, na Reabilitação Funcional são utilizadas diversas técnicas diferentes, como veremos a seguir.
Como funciona a Reabilitação Funcional?
A Reabilitação Funcional atua na área da disfunção através de exercícios controlados, atividades focadas na coordenação entre partes do corpo, treinamento de força, flexibilidade e agilidade, visando preparar o indivíduo para voltar à sua vida cotidiana.
Como auxílio a essas atividades são utilizados acessórios como elásticos, bolas, alteres, cama elástica, cordas e bastões; o objetivo é alcançar o maior volume de estímulos tanto no membro superior, quanto inferior; alcançando todas as rotas metabólicas, mais conhecidas como aeróbicos; condicionando, alongando e fortalecendo de forma progressiva e evoluindo para o trabalho preventivo.
Com a melhoria da força, coordenação e flexibilidade o desempenho dos movimentos também melhora e, assim, os sintomas são aliviados e as atividades do quotidiano do paciente são restabelecidas.
Como se realiza a Reabilitação Funcional?
Para começar o processo de Reabilitação Funcional, o fisioterapeuta deve fazer um levantamento do histórico de lesões, tratamentos e recuperações anteriores para compreender as metas e necessidades do paciente e, assim, montar um plano de reabilitação individual que devolva o paciente à sua vida normal.
São realizados também exames físicos para avaliação de, entre outras coisas, postura, reflexos, caminhada, equilíbrio, controle muscular, estabilização do corpo durante o repouso, a amplitude do movimento das articulações e quaisquer deficiências ou problemas que possam ter contribuído para a lesão original.
Podem ser necessárias ainda tomografia computadorizada, radiografias, ressonância magnética e ultrassonografia para esclarecer o problema ou uma lesão em particular.
Em atletas a reabilitação requer diagnósticos funcionais, como a revisão de suas técnicas, capacidade de movimentos e adaptações secundárias de articulações ou músculos.
Para que o tratamento seja mais eficaz, os exercícios funcionais devem envolver a reabilitação e estabilização muscular de diversas partes do corpo, como abdômen, costas, pescoço, escápula, pelve, quadril, glúteos e músculos adutores.
Para quem a Reabilitação Funcional é indicada?
A Reabilitação Funcional tem sido normalmente aplicada à medicina esportiva no tratamento de atletas. Mas essa abordagem também é benéfica à indivíduos com com complicações e que queiram retornar a sua vida normal, principalmente aqueles que queiram retornar ao trabalho após lesões traumáticas ou neurológicas, como acidentes vasculares cerebrais e acidentes de trânsito, por exemplo.
O objetivo geral do tratamento é preparar o indivíduo para que ele retorne às atividades ou esportes que eram praticados antes da lesão. Ele deve começar assim que essa lesão permitir e deve ser específico para cada caso. O que envolve etapas progressivas de desenvolvimento da força muscular e resistência para o retorno à sua atividade específica.
Qual a diferença entre a Reabilitação Funcional e a fisioterapia clássica?
A principal diferença entre a Reabilitação Funcional e a fisioterapia clássica é foco que cada uma tem no tratamento. Enquanto a fisioterapia clássica foca apenas no tratamento e alívio dos sintomas, a Reabilitação Funcional foca na causa, buscando entender o que causou determinada lesão ou o que motivou um processo inflamatório.
Essa causa pode ser desde uma pisada irregular, fraqueza de estabilizadores de quadril, encurtamento da musculatura posterior da coxa, problemas com a postura até uma perna mais curta que a outra.
Uma vez identificada a causa, todo o tratamento da Reabilitação Funcional é direcionado em resolvê-la. Desse modo, uma vez resolvida, os sintomas desaparecem e as chances do problema voltar são mínimas.
Assim o indivíduo consegue voltar a sua vida normal sem deixar de lado aquilo que tanto gosta por conta de dores e lesões que podem ser resolvidas com o tratamento certo. Sendo a Reabilitação Funcional uma das melhores opções de tratamento dentre todas as outras.
A terapia de ventosa é uma antiga prática de medicina tradicional e complementar. Recentemente, há evidências crescentes de seus benefícios potenciais no tratamento de doenças relacionadas à dor. Este artigo fornece uma visão geral da prática da terapia de ventosa. Além disso, este artigo sugere uma nova classificação dos grupos de terapia de ventosa, uma nova classificação dos eventos adversos de terapia de ventosa e uma classificação atualizada dos tipos de terapia de ventosa.
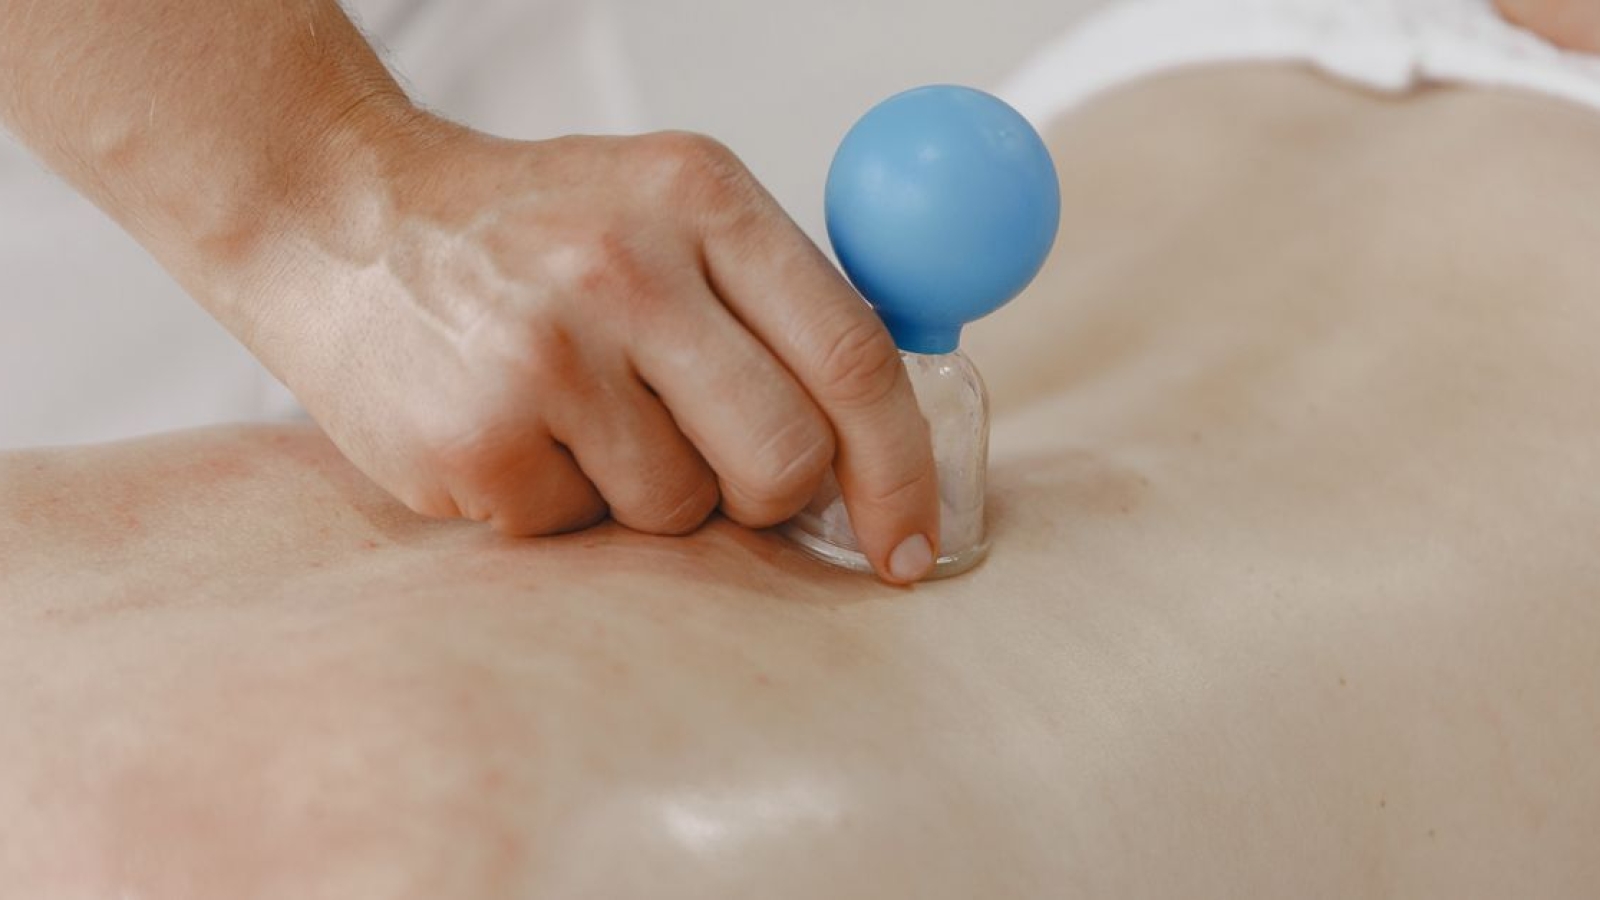
A terapia de ventosa é uma antiga técnica de cura [1] . A colocação é feita aplicando copos em pontos de pele selecionados e criando uma pressão subatmosférica, seja por calor ou por sucção [2] .
O papiro de Eber (1550 aC) do Egito Antigo é um dos textos médicos mais antigos a mencionar a terapia de ventosa. A terapia de cupping faz parte de numerosos sistemas de cura antigos, como o chinês, o Unani , a medicina tradicional coreana, tibetana e oriental [3]. O antigo médico grego Hipócrates compilou extensas descrições do aplicativo de escavação. Ele descreveu dois tipos diferentes de xícaras: uma com uma abertura estreita e uma alça longa e a outra com uma abertura mais larga. O primeiro tipo foi usado para tratar a acumulação profunda de fluidos, enquanto o segundo tipo foi usado para tratar a propagação da dor [4]. A terapia de ventosas foi um tratamento histórico popular nos países árabes e islâmicos. Foi recomendado por médicos árabes e islâmicos como Ibn Sina (980 a 1037 dC), Al-Zahrawi (936 a 1036 dC) e Abu Bakr Al-Razi (854–925 dC). Al-Zahrawi descreveu locais de escavação e ilustrou ferramentas de escavação com diagramas [5] . Ventosaterapia prática da terapia propagação para a Itália e, posteriormente, o resto da Europa entre a 14 ª e 17 ª séculos, durante o Renascimento. Cupping foi um tratamento muito popular de gota e artrite na Itália durante este período [6] .
2 . Mecanismos de ação e efeitos relatados da ventosaterapia
O mecanismo de ação da ventosaterapia não estava claro até agora [7] . Os principais mecanismos de ação propostos foram os efeitos da sucção da pressão subatmosférica, promovendo a circulação sanguínea periférica e melhorando a imunidade. [8] .
Fonte – Aboushanab TS, AlSanad S. Cupping Therapy: An Overview from a Modern Medicine Perspective. J Acupunct Meridian Stud. 2018 Jun;11(3):83-87. doi: 10.1016/j.jams.2018.02.001. Epub 2018 Feb 7. PMID: 29436369.
Ventosaterapia: uma visão geral de uma perspectiva de medicina moderna – Gostou deste Artigo, então confira nosso curso de Ventosaterapia !!
O que é e como ocorre a Doença de Osgood-Schlatter ?
A lesão de Osgood-Schlatter envolve dor e inchaço na pequena saliência óssea na canela (tíbia) logo abaixo da rótula e afeta a área onde ocorre o crescimento ósseo. Muito estresse no osso em crescimento causa dor e inchaço. Essa dor é freqüentemente piorada com a atividade e facilitada pelo repouso.
A principal causa da lesão de Osgood-Schlatter é muita tensão no tendão patelar. A tensão pode ocorrer pelo uso excessivo de esportes, surtos de crescimento ou alinhamento anormal nas pernas. Durante as atividades esportivas, o músculo quadríceps na parte frontal da coxa trabalha, puxando o tendão patelar, que por sua vez puxa a tuberosidade da tíbia. Se esta tensão é muito grande ou ocorre com muita freqüência enquanto o osso está se desenvolvendo, ele pode puxar a área de crescimento da tíbia. Durante os surtos de crescimento, o tendão pode não ser capaz de manter a taxa de crescimento ósseo na parte inferior da perna e pode ficar muito curto. Para o alinhamento anormal, as crianças que estão com os joelhos ou com os pés chatos mudam o ângulo formado entre o músculo quadríceps e o tendão patelar. Este ângulo coloca mais tensão na placa de crescimento da tuberosidade tibial.
O que a fisioterapia pode fazer por esse problema?
A primeira coisa que os fisioterapeutas abordam é aliviar os sintomas. Podemos usar gelo, calor, ultra-som ou estimulação elétrica para ajudar a controlar a inflamação e a dor
Em seguida, trabalhamos com flexibilidade, força e exercícios proprioceptivos para todos os músculos das pernas. Muitas vezes, isquiotibiais apertados e quadríceps colocam um atleta em risco de desenvolver lesões diferentes, portanto, é importante manter uma boa flexibilidade geral. Fortalecemos os músculos da parte inferior da perna e do core para garantir que o atleta tenha um bom equilíbrio muscular no joelho, quadril, tornozelo e núcleo. As atividades de equilíbrio também ajudam a ensinar o atleta a aprender onde seu corpo está no espaço e a usar todos os diferentes músculos das pernas juntos como uma equipe.
A educação postural e os exercícios também são importantes para abordar qualquer alinhamento anormal encontrado. Às vezes, ortóteses, ou inserções de sapato, são necessárias para ajudar a corrigir posições planas ou batidas
Finalmente, quando os sintomas diminuem, os terapeutas trabalham em atividades esportivas específicas e padrões de movimento, a fim de ajudar a melhorar a forma e reduzir a tensão no joelho durante esportes.
Os Benefícios Liberação Miofascial são inumeráveis. Como a Liberação Miofascial é eficaz em vários níveis da estrutura interna (superficial, intermediária, profunda / celular), pode beneficiar as condições em todos os níveis. Se você está sofrendo de dor superficial, dor mais profunda dentro de um músculo ou articulação, ou disfunção celular, Liberação Miofascial pode oferecer algum benefício *.
Complementar outras terapias: Liberação Miofascial é um ótimo complemento para outros regimes de tratamento. Por exemplo, no caso do tratamento quiroprático, a adição de MFR pode garantir que os ajustes quiropráticos “fiquem” e não voltem a ocorrer assim que você sair do seu fisioterapeuta. No caso de suplementos nutricionais ou medicamentos, a MFR pode garantir que eles atinjam efetivamente a meta pretendida e afetem seu benefício total. Afinal, se uma determinada glândula ou órgão não estiver funcionando adequadamente devido a uma restrição fascial que a privará de nutrição vital, nenhuma quantidade de medicamento ou suplemento mudará se estiver sujeita às mesmas vias internas de entrega afetadas pela restrição.
Lesões por Movimentos Repetitivos: A liberação miofascial também é efetiva para Lesões por Movimentos Repetitivos. Em tais casos, MFR pode criar espaço em torno de ligamentos afetados para aliviar a inflamação naturalmente sem medicação ou cirurgia. Seja a síndrome do túnel do carpo, cotovelo de tenista ou qualquer número de condições de ombro e joelho, o MFR pode aliviar naturalmente e suavemente a tensão nos tecidos conjuntivos que cercam as articulações e, quando apertadas, irritam e impedem o movimento natural dos ligamentos e causam inflamação.
Disco Bulboso ou Herniado: Liberação Miofascial pode descomprimir a coluna. Isso tira a pressão do disco, alivia a dor associada e cria espaço para o disco curar naturalmente. Isso pode eliminar a necessidade de cirurgia nas costas para reparar um disco e evita horas de desconforto sentado ou em pé em um dispositivo de tração.
Disfunção Temporal da Articulação Mandibular: A Liberação Miofascial pode liberar a tensão dos tecidos adjacentes que comprimem ou impedem a função da ATM. Esta liberação pode devolver a TMJ à sua amplitude de movimento adequada e eliminar o desvio lateral, o clique e a dor.
Prejuízo: A Liberação Miofascial pode resolver os resultados diretos e indiretos das lesões. Muitas vezes, os danos ocorrem não apenas à vista de um impacto primário, mas também dos impactos subsequentes que ocorrem posteriormente. Por exemplo, no whiplash, o cérebro impacta primeiro o crânio em uma direção, depois a outra. No caso de uma queda, o primeiro impacto é uma parte do corpo que encontra o chão. . . impactos subsequentes ocorrem onde a onda de choque termina em outro lugar do corpo. Como o MFR é uma terapia de todo o corpo, ele pode ajudar a localizar e liberar restrições relacionadas em locais diferentes do local de impacto inicial. Este conceito nem é considerado pela maioria dos médicos. Depois, há lesões secundárias causadas pelos ferimentos primários. Por exemplo, depois de quebrar o tornozelo e ficar confinado a uma cadeira de rodas, você desenvolve dor ciática. Ou, depois de usar muletas por uma semana, você desenvolve dor no ombro / pescoço. Depois, há as síndromes de dor que resultam dos padrões de manutenção a longo prazo. Após uma lesão, seu corpo adota uma postura protetora projetada para proteger a área lesada. Embora essa postura seja inicialmente consciente, após cerca de três dias, ela fica entranhada no subconsciente. Esse padrão de retenção subconsciente permanece por muito tempo depois que uma lesão cura e perpetua um estado de desequilíbrio no corpo. Desequilíbrio a longo prazo no corpo pode levar a dor e lesões adicionais. Por exemplo, após um tornozelo torcido, seus quadris podem ficar desequilibrados. Este desequilíbrio nos quadris é compensado por uma curvatura lateral da coluna (escoliose), é refletida nos ombros, e finalmente resulta em uma compressão lateral de um disco entre duas vértebras no pescoço e um desalinhamento entre o crânio e a primeira vértebra cervical. Consequentemente, você acaba com dores de cabeça crônicas e dor no pescoço e ombros – tudo por causa do tornozelo torcido. A abordagem MFR pode decodificar esses padrões e restaurar o equilíbrio e o movimento do corpo – deixando você mais leve, estável e sem dor.
Dor ciática: Liberação Miofascial pode tirar a pressão do nervo ciático. Seja causada pela compressão da coluna lombar ou pelo impacto do músculo piriforme, o MFR pode criar o espaço necessário para que as articulações e os músculos ao redor funcionem sem afetar o nervo ciático e causar dor.
Cefaleia Crônica / Enxaqueca: Liberação Miofascial pode tirar a tensão das áreas sensíveis à dor na base do crânio, o que pode levar à dor de cabeça crônica. O MFR também pode remover a tensão das estruturas fasciais no interior do crânio, o que pode levar à enxaqueca.
Disfunção da glândula e doença relacionada:Liberação miofascial pode liberar tensão / restrições no tecido que envolve as glândulas que podem aplicar pressão, restringir o movimento ou impedir o fluxo de nutrição para as glândulas dentro da cabeça. O tecido fascial alinha a cavidade craniana e divide as duas metades do cérebro. Sempre que ocorrem restrições neste tecido, a função adequada das glândulas associadas, e até mesmo do próprio cérebro, pode ser inibida. Ao liberar essas restrições, o MFR pode restaurar a função adequada.
Trauma: O trauma ocorre sempre que o centro de controle de nosso cérebro (cérebro límbico) fica sobrecarregado de estímulos sensoriais. Quer seja abuso emocional / físico / sexual, trauma militar, um encontro que muda a vida, etc., quando o cérebro límbico é subjugado, o input sensorial é desviado do cérebro cognitivo superior para o cérebro inferior e primitivo. Este cérebro inferior é responsável pelo comportamento instintivo e controla a nossa resposta “lutar / fugir / congelar”. O cérebro primitivo também incorpora o sistema nervoso periférico (medula espinhal e nervos). À medida que a entrada sensorial e o controle da decisão são desviados do cérebro superior, todo registro do trauma, emoções associadas e comportamento / resposta resultante não reside no cérebro superior, mas no corpo. MFR é uma terapia física e energética que pode liberar esses registros – emoções e memórias – dos tecidos do corpo. Uma vez liberados no sistema fascial maior, eles podem ser disponibilizados para processamento cognitivo e resolução. Por este motivo, pode ser muito eficaz incorporar o MFR no seu regime de cura de trauma, onde pode complementar a terapia cognitiva e torná-la drasticamente mais eficaz.
Confira um video sobre o Benefícios Liberação Miofascial
Confira esse artigo completo sobre os Benefícios da Liberação Miofascial
Efeitos da Liberação Miofascial Sobre a Flexibilidade: uma Revisão Sistemática
As evidências contemporâneas sobre os ganhos de flexibilidade em função da técnica de liberação miofascial ainda apresentam resultados inconclusivos. Portanto, o objetivo do presente estudo foi revisar, de forma sistemática, as evidências sobre os efeitos da liberação miofascial sobre os ganhos de flexibilidade. A busca dos artigos foi realizada no Google Acadêmico até maio de 2017, com a aplicação dos seguintes descritores “liberação miofascial”, “flexibilidade” e “foam roller”. Foram encontrados 22 artigos e após a aplicação dos devidos critérios de inclusão e exclusão, quatro investigações apresentaram elegibilidade para compor a presente revisão. As evidências encontradas, de maneira totalitária, apontam a eficiência da liberação miofascial em promover aumento nos ganhos de flexibilidade, seja de forma aguda ou crônica. Sendo assim, sob a égide das evidencias em tela, sugere-se a liberação miofascial como uma estratégia pertinente e eficiente, em sua aplicação, no que diz respeito aos ganhos de flexibilidade. (AU).


 Cart is empty